-

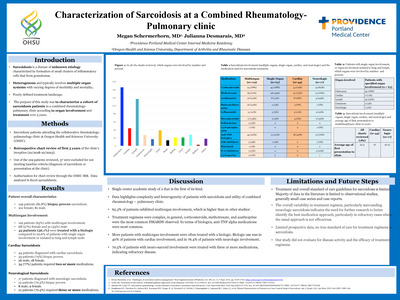
Characterization of Sarcoidosis at a Combined Rheumatology-Pulmonary Clinic
Megan Schermerhorn, MD and Julianna Desmarais, MD
Introduction: Sarcoidosis is a disease of unknown etiology characterized by formation of small clusters of inflammatory cells that form granulomas. Heterogenous and typically involves multiple organ systems with varying degrees of morbidity and mortality. Poorly defined treatment landscape. The purpose of this study was to characterize a cohort of sarcoidosis patients in a combined rheumatology-pulmonary clinic according to organ involvement and treatment over 5 years. Discussion: •Single center academic study of a that is the first of its kind. •Data highlights complexity and heterogeneity of patients with sarcoidosis and utility of combined rheumatology – pulmonary clinic. •65.3% of patients exhibited multiorgan involvement, which is higher than in other studies. •Treatment regimens were complex, in general, corticosteroids, methotrexate, and azathioprine were the most common DMARDS observed. In terms of biologics, anti-TNF alpha medications were most common. •More patients with multiorgan involvement were often treated with a biologic. Biologic use was in 40% of patients with cardiac involvement, and in 76.4% of patients with neurologic involvement. •70.5% of patients with neuro-sarcoid involvement were treated with three or more medications, indicating refractory disease. Limitations and Future Steps: •Treatment and overall standard of care guidelines for sarcoidosis is limited. Majority of data in the literature is limited to observational studies, generally small case series and case reports. •The overall variability in treatment regimen, particularly surrounding neurologic sarcoidosis indicates the need for further research to better identify the best medication approach, particularly in refractory cases where the usual approach is not efficacious. •Limited prospective data, no true standard of care for treatment regimens in sarcoidosis. •Our study did not evaluate for disease activity and the efficacy of treatment regimens.
-

The Differential Expands: Ataxia from Paraneoplastic Cerebellar Degeneration
Dominic Thomas, MD and Amy Dechet
Introduction: Paraneoplastic cerebellar degeneration is a rare cause of cerebellar ataxia with a poor prognosis for neurologic recovery. The management of symptoms is dependent primarily upon timely diag-nosis and treatment of the underlying neoplasm. Herein, we present the diagnostic and treatment course of a patient with paraneoplastic cerebellar degeneration. Case: A 72-year-old woman with a past medical history of left mastectomy for high grade ER/PR negative Her2 positive invasive ductal carcinoma presented with progressively worsening dysarthria and ataxia over two months. A metabolic work up by her primary care physician was unrevealing. Breast MRI did not show recurrence of her cancer. During her visit with her oncolo-gist, the patient noted a ten-pound weight loss. At her first emergency department visit, exam revealed dysarthria but was an otherwise normal neurologic exam. MRI brain without contrast and MRA head and neck without contrast showed no evidence of ischemia, hemorrhage or mass effect. She was discharged home with the plan to follow up with outpatient neurology. Three days later, the patient presented to another emergency department and was found to be dysarthric but otherwise neurologically intact. CT head without contrast and CTA head and neck did not reveal a structural cause. MRI with and without contrast noted a non-specific T2 FLAIR hyperin-tense signal associated with the sulci or surface of the cerebellum. CSF showed elevated protein twice the upper limit of normal and a higher-than-normal fraction of lymphocytes. During her hospitalization she was noted to have worsening dysarthria, bilateral upper and lower extremity ataxia and development of diplopia for which she received 500mg methylprednisolone twice daily for three days and IVIG for five days. Symptoms were initially responsive but progressed further prompting five days of plasmapheresis. Symptoms did not remit. CA-125 was elevated at 253 U/mL and the CSF paraneoplastic panel was positive for anti-Yo antibody at 1:61440. A PET CT detected two para-aortic lymph nodes. Pathology from a total abdominal hysterectomy and bilateral salpingo-oophorectomy, peritoneal washing, and singular lymph node removal yielded carcinoma of mullerian origin in the lymph node alone. Steroids and cyclophosphamide were trialed for persistent neurologic symptoms. She received two cycles of docetaxel and carboplatin. The patient's care was transferred to a facility closer to family. Discussion: Paraneoplastic cerebellar degeneration is a rare cause of subacute cerebellar ataxia with an inci-dence of 0.41-0.89/100,000 person years2,3. Associated malignancies include most commonly small cell lung cancer, ovarian cancer, breast cancer and Hodgkin lymphoma. While several auto-antibodies have been identified as drivers of cerebellar degeneration, the anti-Yo antibody is predominantly associated with gynecological and breast cancers. Greater than 90% of these can-cers identified while alive or on autopsy4. Brain MRI rarely shows cerebellar enhancement, as seen in the described patient, and more typically is normal or shows cerebellar degeneration. Anti-Yo (purkinje cell cytoplasmic antibody type 1) can be detected in serum or CSF. It is the most commonly associated antibody intracellularly targeting the cerebellar degeneration-related 2-like (CDR2L) antigen within the Purkinje cells of the cerebellum6. When bound, it leads to cell death by inhibiting the ribosome to which it is bound. Once the diagnosis of paraneoplastic cerebellar ataxia is suspected, it is important to search for the source of the neoplasm since the most effec-tive antidote is treating the primary malignancy. Unfortunately, 75-80% of patients become and remain non-ambulatory with this condition, with delay of diagnosis likely contributing to poor outcomes4. There are anecdotal reports of neurologic improvement with IVIG, plasmapheresis, steroids, azathioprine, cyclophosphamide, and rituximab5. Albeit rare, it is important to be highly suspicious of autoantibody mediated neuronal degenerative diseases as symptom management depends on timely diagnosis and treatment. Conclusion: When work-up for more common causes of cerebellar ataxia is negative and/or if a paraneoplastic source is suspected, imaging and CSF testing can guide further evaluation. Once the diagnosis of para-neoplastic cerebellar ataxia is suspected, it is important to search for the source of the neoplasm since the most effective antidote is treating the primary malignancy. Albeit rare, it is important to be highly suspicious of autoantibody mediated neuronal degenerative diseases as symptom management depends on timely diagnosis and treatment
Printing is not supported at the primary Gallery Thumbnail page. Please first navigate to a specific Image before printing.