-

Implementation of Routing CYP2C19 Pharmacogenetic Testing to Guide Antiplatelet Therapy Post-Percutaneous Coronary Intervention
Stephanie Chan
A P2Y12 inhibitor with aspirin is recommended in the post-PCI setting with stent implantation. Clopidogrel requires hepatic biotransformation to generate an active metabolite which inhibits platelet aggregation however the most prominent enzyme, CYP2C19, is a highly polymorphic gene that results in wide range of responses. Poor CYP2C19 function can lead to suboptimal clinical outcomes and increased thrombotic risk but despite this variability, clopidogrel is consistently used without routine testing. The process to be implemented is routine genetic testing in patients started on clopidogrel to optimize effectiveness and safety of their treatment while aligning with current clinical guidelines and best practices. A weekly review will be conducted to identify patients who were initiated on clopidogrel therapy. Eligible patients will be scheduled for an in-person or telephonic visit with a clinical pharmacist and during this appointment, a shared decision-making conversation will be held where patients will receive education about pharmacogenomic testing including the testing process, associated costs, and potential benefits and risks. Patients who agree to the test will undergo pharmacogenomic testing and the sample will be sent to a testing lab for processing. Once available, the pharmacist will analyze the results and provide a recommendation to the patient’s primary care provider in the form of a consult whether the patient is indicated to continue clopidogrel or switch to an alternative antiplatelet therapy with ticagrelor or prasugrel. The recommendation will be based on the patient's predicted phenotype of ultra-rapid, rapid, normal, likely intermediate, intermediate, likely poor, or poor metabolizer based on the genotype results and the current Clinical Pharmacogenetics Implementation Consortium (CPIC) guideline recommendations.
-
Patient Forms in Their Native Written Languages
Bin Chen and Monica DeMasi
Problem Statement: Patients who speak languages other than English lack access to forms in their preferred language. Current translation methods (using interpreters) are time-consuming and may influence patient responses. At our clinic in Southeast Portland, approximately half of our visits involve translators for non-English-speaking patients. While we strive to use translators to assist patients with their English forms, this creates a disparity in the care we can provide for the following reasons. Firstly, the in-person translators we employ are part of the same small communities as most of our patients, leading to potential inaccuracies in describing social or sexual health concerns. As a large health system, we should aim for inclusivity and in accommodating patients’ diverse language skills. Written forms in patient’s native language is a good first step toward alleviating the language barrier all our patients face 1. Providing written information in the patient’s native language in addition to translators help with discussion of care can enhance the care received from providers.2 Objectives: Project Objective: How to obtain wellness forms, PHQ-9 and GAD-7 in our top 5 languages and exploring a clinic workflow to ensure these are appropriately given out. Methods: 1. Translate standard adult wellness forms ages 18-64 to written Chinese, Spanish, 2. Vietnamese, and Russian. AI translation services was used instead of Linguava due to the cost of about $200 per page. 3. Obtaining approved PHQ-9 form translations in Chinese, Spanish, Vietnamese, and Russian. Found this on OR Dial. 4. Explore workflow for optimization so that language congruent written forms are given to non-English speakers appropriately. Made protopage that links to Sharepoint 5. documents for all the forms we routinely use in other languages. Results: See Figures in the poster for website created and forms translated. Survey to show staff of this new website showed that having a clinic discussion in about 5 minutes increased awareness by > 40% (see Figure 3 and 4) Discussion/Conclusions/Next Steps: An overview of SE clinic patient population demographics and visit types indicated a potential for making care provided more equitable by having forms in patient’s native language. This is important because studies have shown that having these forms increases response rates3 and quality of information to allow the clinician to provide better care2. It is currently not cost effective for a single clinic such as PMG Southeast to pay for human translation of all the forms regularly used, but preliminary translation with the use of readily available AI translation such as Deep L showed that this technology can be fairly accurate and cost effective. Future Plans: • Consider adding more forms such as patient education documents, pediatric forms, and instructions for FIT tests • Dual language forms for MA interpretation of all the forms • Work with local leadership in getting formal translation of all forms • Consider piloting AI translation for After Visit Summaries • Formalizing a workflow in Southeast for PRRs and medical assistants to find the necessary forms for our patients.
-
QI: Improving Rates of Amblyopia Screening via GoCheck Kids Photoscreening At PMG Southeast Family Medicine Clinic
Zhong Bin Chen, Mai'ana Feuerbone, Tiffany Nguyen, and Ben Peterson
Background Amblyopia (also known as “lazy eye”) is a condition that can develop when one eye has poor vision. The brain then favors the stronger eye and ignores the input from the eye with weaker vision. This can prevent further development of the affected eye, possibly resulting in permanent vision loss. The prevalence of amblyopia in the United States is 1 to 6 percent, and considered to be a major public health problem. If left untreated, amblyopia can lead to problems in school as well as permanent vision loss in the affected eye. To avoid the effects of this disease, amblyopia must be diagnosed and treated in early childhood. Recovery of amblyopic eye is maximum when initiated before the age 3 and decreases with age. Instrument based photoscreening can be used at an earlier age than traditional visual acuity wall charts, which is advantageous for prompt referral and treatment. Photoscreeners have been studied and found to be effective in detection of amblyogenic risk factors. GoCheck kids is a smartphone-based screening tool that takes a picture of the eyes and analyzes the red light reflex for amblyogenic risk factors. Due to the increased sensitivity of the test, photoscreening is recommended by the USPSTF, AAP, and AAFP. Our clinic previously did not have any data on current rates of photoscreening as we did not have any implemented workflow. Objectives Increase rates of photoscreening with GoCheck Kids to 75% of well child checks in patients ages 12 months to 36 months by March 2025. Methods The first PDSA involved learning the GoCheck Kids (GCK) Technology, its indications, and feasibility in clinic. We learned how to use GCK and the official Providence workflow. Our QI group learned GCK independently with Provi-dence information and their website. For the second PDSA, we gave a presentation about GCK at the clinic all staff meeting. The presentation outlined the importance of amblyopia screening and when and how to utilize the GCK application. We assessed staff knowledge with a pre and post survey and also opened discussion to potential concerns with starting this workflow at our clinic. For the third PDSA, we decided to observe the Scholls Pediatrics clinic, a pediat-ric clinic that was frequently using the GCK photoscreening application and had streamlined the workflow. We were then able to adapt a similar workflow and created a visual diagram outlining specific roles for both MA’s and providers. We presented this updated workflow at the clinic all staff meeting.
-
Effect of Analgesia-first Sedation on Sedative Exposure and Clinical Outcomes in a Medical Intensive Care Unit
Daniel Cicarelli, PharmD; Gideon Berdahl, PharmD; Christopher Cheun, PharmD; Linda Huynh, PharmD; Lianne Lin, PharmD; and Sarah Teachey, PharmD
Abstract: Utilizing analgesia-first over sedation-first strategies in mechanically ventilated (MV) patients is recommended by the Society of Critical Care Medicine and is associated with improved outcomes, including more ventilator-free days and reduced intensive care unit (ICU) and hospital lengths of stay (LOS). Adequate pain control reduces agitation and discomfort, thereby decreasing the need for deeper sedation. This single-center, retrospective cohort study aims to describe current analgesia-first sedation practices in the medical ICU and evaluate their impact on sedative requirements and clinical outcomes. Adult patients (≥18 years) admitted to Providence St. Vincent Medical Center and mechanically ventilated for ≥24 hours between October 1, 2022, and September 30, 2024, will be included. Epic Slicer Dicer will be used for patient identification, and REDCap for data collection. Exclusion criteria include comfort care status, ICU LOS < 24 hours, MV duration >7 days, use of continuous paralytics or epidural analgesia, or deep sedation (e.g., status epilepticus). Patients will be categorized into quartiles based on the distribution of predefined analgesia-first actions, guided by objective measures such as the Critical-Care Pain Observation Tool (CPOT) and Richmond Agitation-Sedation Scale (RASS) scores. The primary outcome is time to extubation (hours). Secondary outcomes include ICU LOS, 30-day mortality, and mean cumulative analgesic and sedative doses per patient, median RASS scores, CPOT scores, incidence of reintu-bation within 24 hours, and incidence of delirium. Data collection will include baseline characteristics, relevant comorbidities, baseline Sequential Organ Failure Assessment (SOFA) scores, MV duration, ICU and hospital LOS, 30-day mortality, and pain and sedation metrics. The primary outcome will be analyzed using ANOVA, and secondary outcomes will be assessed with Wilcoxon rank-sum or Student’s t-tests, depending on data normality. A p-value < 0.05 will be considered statistically significant. Results and conclusions will be reported upon project completion. (IRB approved) Learning Objectives: 1. Explain the rationale and clinical benefits of an analgesia-first sedation strategy in mechanically ventilated patients. 2. Describe the study design and methods used to evaluate sedation practices in the ICU setting. 3. Assess the impact of analgesia-first sedation on clinical outcomes such as time to to extubation, ICU length of stay, and sedation requirements. Presentation Category: Critical Care
-

Immune Checkpoint Inhibitors: Friend or Foe
Antonio Cordova, Jesse Powell, Whitney Elg-Salsman, and Caroline McCulley
Introduction: • Many cancers use mechanisms to escape killing by the immunesystem. • Cancer cells can mimicimmune checkpoint proteins such as cytotoxic T lymphocyte–associated antigen 4 (CTLA-4) ligand and the programmed death1 receptor ligand (PD-L1) toinhibit the T-cell response. • Immune checkpoint inhibitors (ICI's) are a novel set of monoclonalantibody cancer therapies. • ICI'sblockcheckpoint proteins from binding with their partner proteins oncancer cells thus allowing T-cells to kill tumor cells. • ICIs have promising anti-cancer results. • ICIs are also associated with immune related adverse events(irAEs), including dermatitis, pneumonitis, colitis,hepatitis, nephritis. • A rare but seriousirAEisICI-associated myositis causing bulbar and respiratory muscle weakness. Case Presentation: HPI: 68 y/o with metastatic renal cell carcinoma presenting with 3 days proximal muscle weakness, inability to walk, diffuse severe myalgias, shortness of breath, hoarse voice, and dysphagia. PMH: Complete Heart block status post pacemaker placement ~8 days ago Medications • Completed course of Pembrolizumab(ICI) • Recently initiated Nivolumab (ICI) and Cabozantinib (VEGF-I) Physical exam • Neuro: Weak jaw, weak shoulder shrug, 3/5 hip flexion/extension; 4/5 knee flexion/extension,4/5 ankle plantarflexion/extension, 4/5 grip strength. • Skin: no skin rash including heliotrope,shawl sign, gottron's papules/sign • MSK: No joint tenderness or synovitis Pertinent Labs: • ESR 24 • CRP 33 • CK 5124 • Troponin >5000 • Myositis specific antibody panel: negative • ANA: negative • Muscle specific kinase ab: negative • Myasthenia/LEMs panel: negative Additional studies: EMG: Prominent muscular fibrillations and positive sharp waves Repetitive nerve stimulation (RNS): No Defect of Neuromuscular transmission Discussion Serious Immune-related adverse can occur in up to 25% of patient's undergoing ICI therapy • ICI's trigger non-specific T-cell activation leading to off-target irAE's including this case of myositis • There are several mechanisms proposed for irAE's, but the pathogenesis of ICI induced myositis is still not fully understood • Typical autoimmune myositis (dermatomyositis, polymyositis) has an indolent course and does not involve bulbar or respiratory muscles. • ICI myositis is rapidly progressive and can cause bulbar and respiratory muscle weakness, mimicking myasthenia gravis (MG). • Myocarditis and MG-like symptoms present in ~10-15% ICI myositis cases. • When myocarditis and MG-like symptoms are present mortality is as high as 60%. • Overall ICI Myositis is a diagnosis of exclusion and workup should rule out Primary inflammatory myositis and Myasthenia Gravis, however treatment should be initiated as soon as possible due to the high morbidity and mortality rate
-
Utilization patterns of MRSA NAAT withing regional health system
Joseph Dang, PharmD; Emily Fox; and Greg Tallman
Abstract: Methicillin-resistant Staphylococcus aureus (MRSA) nucleic acid amplification tests (NAATs) have shown excellent negative predictive value for clinical MRSA infection and have consistently been shown to reduce vancomycin use. However, in many infections the prevalence of MRSA is sufficiently low that the MRSA NAAT may not be diagnostically useful, creating the potential for overutilization. The purpose of this project is to identify MRSA NAAT usage patterns in the Oregon region of a national health system. This is a multi-center, retrospective analysis of patients aged 18 or older who received an IV vancomycin treatment course between May 30, 2021 and November 30, 2023 and had a MRSA NAAT collected within the Oregon region of this health-system. The first objective is to describe how MRSA NAATs are being used within the Oregon region of this health system; the primary outcome will be mean time to de-escalation. Demographics, medication, microbiology, laboratory, and hospitalization data will be extracted electronically. Descriptive statistics will be used to describe baseline characteristics of the study population. Student’s t-test will be used to analyze the mean time to vancomycin de-escalation if normally distributed, otherwise Wilcoxon rank-sum. Results and Conclusions will be shared when the project is complete. (IRB approved)
-
Nutrition Elective Impact on Resident Competency
Andrew W. Duchesne, Jill Christensen, Heidi Davis, Kara Castro, and Charlotte Navarre
Context/background: Nutrition is the number one risk factor contributing to death in the United States, and yet healthcare providers report not receiving ade-quate education to provide effective patient counseling. Primary care providers are perfectly situated in the healthcare continuum to provide evidence-based nutrition-al counseling to patients, as well as screen for and intervene on food insecurity. Objective: Main objective: evaluate the impact of a structured nutritional elective on Family Medicine residents’ competency regarding evidence-based nutritional counseling. Secondary objective: evaluate impact on competency screening for and intervening on food insecurity. Methods: Design: pre- and post-elective survey evaluating 5 domains on a scale of 1-5 (1 being low, 5 being high): 1) knowledge of key nutritional requirements and evidence-based recommendations, 2) comfort providing data/statistics around diet-related health complications and counseling about specific dietary needs, 3) comfort screening for food insecurity, 4) knowledge to intervene on food insecuri-ty, 5) knowledge of Providence-specific resources for food insecurity and how to access them. Setting: Providence Milwaukie Community Teaching Kitchen Participants: 4 family medicine residents from Providence Milwaukie Intervention: structed elective consisting of at least 7 half days. First half day is 4-hour online CME course through Gaples institute: Nutrition Science for Health and Longevity: What Every Physician Needs to Know. Subsequent half days spent rotating with Providence Milwaukie Teaching Kitchen, including time with Regis-tered Dietitian/Certified Diabetes Care and Education Specialist, Patient Navigator screening and addressing food insecurity, food pharmacy distribution, working in community garden, participating in culinary medicine classes. Results: Post-elective survey showed statistically significant improvement across all domains (all with p-values < 0.05). Averages for the following domains [pre -> post]: 1) [1.5 -> 4.5], 2) [ 1.5 -> 4], 3) [2 -> 5], 4) [2.25 -> 5], 5) [2 -> 5]. Discussion/conclusions: Nutrition is one of the most important factors affecting our patients’ health, and yet many providers do not feel adequately trained to coun-sel patients effectively. A structed nutrition elective was shown to improve family medicine resident competency providing evidence-based nutrition recommenda-tions. Secondarily, it was also shown to improve comfort screening for and knowledge of how to intervene on food insecurity.
-
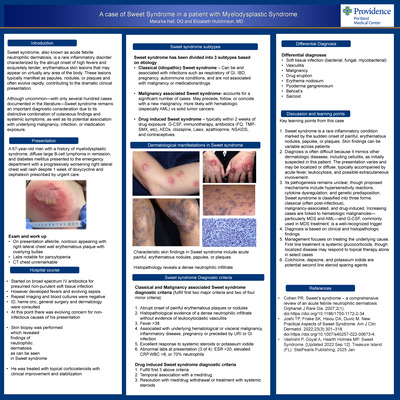
A Vexing Case: A Newly Discovered Autoinflammatory Disease
Ashley Edwards, MD and Caroline McCulley
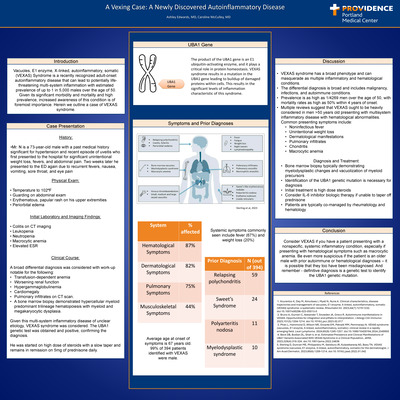
Introduction: Vacuoles, E1 enzyme, X-linked, autoinflammatory, somatic (VEXAS) Syndrome is a recently recognized adult-onset autoinflammatory disease that can lead to potentially lifethreatening multi-system inflammation with estimated prevalence of up to 1 in 5,000 males over the age of 50. Given its significant morbidity and mortality and high prevalence, increased awareness of this condition is of foremost importance. Herein we outline a case of VEXAS syndrome. Case Presentation: Mr. N is a 73-year-old male with a past medical history significant for hypertension and recent episode of uveitis who first presented to the hospital for significant unintentional weight loss, fevers, and abdominal pain. Two weeks later he presented to the ED again due to recurrent fevers, nausea, vomiting, sore throat, and eye pain. Given this multi-system inflammatory disease of unclear etiology, VEXAS syndrome was considered. The UBA1 genetic test was obtained and positive, confirming the diagnosis. He was started on high dose of steroids with a slow taper and remains in remission on 5mg of prednisone daily. Discussion: VEXAS syndrome has a broad phenotype and can masquerade as multiple inflammatory and hematological conditions. The differential diagnosis is nj8broad and includes malignancy, infections, and autoimmune conditions. Prevalence is as high as 1/4269 men over the age of 50, with mortality rates as high as 50% within 4 years of onset. Multiple reviews suggest that VEXAS ought to be heavily considered in men >50 years old presenting with multisystem inflammatory disease with hematological abnormalities. Common presenting symptoms include: • Noninfectious fever • Unintentional weight loss • Dermatological manifestations • Pulmonary infiltrates • Chondritis • Macrocytic anemia Diagnosis and Treatment: Bone marrow biopsy typically demonstrating myelodysplastic changes and vacuolization of myeloid precursors. Identification of the UBA1 genetic mutation is necessary for diagnosis. Initial treatment is high dose steroids. Consider IL-6 inhibitor biologic therapy if unable to taper off Prednisone. Patients are typically co-managed by rheumatology and hematology
-
Legionella: an infectious cause of rhabdomyolysis-associated acute renal failure
Alexander Hall, MD and Meera Jain
Introduction: Legionella species are gram negative bacteria that cause pneumonia both sporadically and in outbreaks. Infection with Legionella can result in multisystem illness with extrapulmonary manifestations including abdominal pain, diarrhea, headache, encephalopathy, hyponatremia, and liver injury. Renal injury from legionellosis is less common. Here, we present a case of legionella-associated rhabdomyolysis resulting in acute renal failure secondary to heme pigment nephropathy despite unimpressive muscle enzyme levels. Case Presentation: A 56-year-old previously healthy male presented with one week of fatigue, fever, generalized abdominal pain, and shortness of breath. Initial vital signs were significant for temperature of 39.0 °C, heart rate of 115, blood pressure of 123/74, respiratory rate of 28/min, and SpO2 90% on room air. His creatinine was 14.8, blood urea nitrogen (BUN) 105, bicarbonate 15 with anion gap of 22, sodium of 126, and creatine kinase (CK) 6528. There was mild elevation of his liver function studies. Chest X-ray revealed a left lower lobe infiltrate. This was overall consistent with sepsis secondary to lobar pneumonia and associated hypoxemic respiratory failure, acute oliguric renal failure with uremic metabolic acidosis, hyponatremia, and transaminitis. He was started on ceftriaxone and azithromycin for community acquired pneumonia as well as IV fluids. Legionella pneumophila urine antigen returned positive on hospital day 2, confirming the diagnosis of Legionellosis. A broad workup was performed for the cause of renal failure. This included strongly positive urine myoglobin and renal biopsy with findings of heme pigment-induced acute tubular injury. The patient was treated with two days of hemodialysis on hospital days 4 and 5 to correct acidosis and uremia. Renal function and urine output improved without need for further dialysis. His creatinine was 2.17 and BUN 38 on discharge. The lobar pneumonia and hypoxemia resolved with an extended course of azithromycin transitioned to levofloxacin. The source of legionella was never identified by the local health department. Discussion: This case highlights acute renal failure secondary to rhabdomyolysis, a rare complication in patients with Legionella pneumonia. Although acute kidney injury in rhabdomyolysis is typically associated with admission CK levels >15000, it can occur with CK levels as low as 5000 in the presence of additional insults such as sepsis, dehydration, or acidosis. This was the case in this patient, who had a presenting CK level of 6528. The mechanism of rhabdomyolysis in Legionellosis is poorly understood but is thought to be related to either direct muscle infection or indirect muscle injury related to bacterial toxin, with contributing factors of fever, rigors, and hypovolemia. Prior descriptions of legionella-associated rhabdomyolysis and renal failure are limited to case reports and literature reviews
-
Comparing Length of Stay Between Adult Patients Admitted to the Intensive Care Unit With Alcohol Withdrawal Syndrome Treated with Phenobarbital versus Lorazepam
M Cate Hoye
Introduction: Syphilis has long been known as the great imitator due to its variety of presenting symptoms and organ systems affected. Rationale: Alcohol withdrawal syndrome (AWS) is a common reason for hospital and intensive care unit admissions. Standard of care for treatment of AWS includes use of benzodiazepines (e.g. lorazepam). However, due to the high incidence of AWS in hospitalized patients, and therefore burden on hospital systems, there is interest in identifying more effective treatments. Phenobarbital, a barbiturate, is a safe alternative to benzodiazepines for AWS that has several benefits including its mechanism of action and pharmacokinetics. Methods: We queried the medical record system to review admission data for patients admitted to the ICU for AWS during a 34-month period to determine if there was a difference in length of stay (LOS) between patients who received benzodiazepines versus those who received phenobarbital. Patients were included if they were admitted to the ICU, with a diagnosis of alcohol use disorder, on clinical institute of alcohol withdrawal (CIWA) scoring, who did not have a diagnosis of epilepsy. Simple regression analysis was used to determine associations between LOS and phenobarbital amount, lorazepam amount, and complications (mechanical ventilation). Results: 204 patients were included in the study. 112 patients (52.90%) received phenobarbital and had a mean hospital LOS of 11.82 days (median 8.34 days, SD 9.73) and a mean ICU LOS of 6.91 days, with an average dose of phenobarbital of 11.77 mg/kg. All the patients who received phenobarbital also received lorazepam (average amount 151.08 mg). 87 patients (42.65%) received only lorazepam and had a mean hospital LOS of 10.14 days (median 6.05 days, standard deviation 15.18), mean ICU LOS of 3.39 days, with an average amount of lorazepam of 53.95 mg. There was no significant difference between LOS for patients who received phenobarbital and those who received only lorazepam (p = 0.37). Conclusions: There was no significant difference in LOS between patients who received lorazepam versus those who received phenobarbital for AWS. Additionally, all the patients who were treated with phenobarbital were also treated with lorazepam which increases the risk of respiratory depression (a side effect of both medications). This finding presented an opportunity to develop an initiative to standardize care by establishing a consistent protocol for phenobarbital use in the ICU. We identified severity of withdrawal as a confounder: often patients with the highest CIWA scores received both phenobarbital and lorazepam; suggesting that phenobarbital is safe, but protocols informing its use would improve patient safety and potentially LOS.
-
Pneumocystis Jirovecii Pneumonia in an Immunocompetent Women: A Case Report
M Cate Hoye
We present the Pneumocystis jirovecii pneumonia (PCP) case of an 89-year-old female with a past medical history of meningioma resection. The patient completed a 22-day steroid taper 7 days before presenting with acute hypoxemic respiratory failure. CT chest on admission revealed ground glass opacities. While PCP was considered, community acquired pneumonia (CAP) was felt to be more likely due to the short course of steroids. Failure to improve with CAP treatment ultimately prompted bronchoalveolar lavage, revealing PCP. Prophylaxis for PCP is recommended in patients receiving greater than or equal to 20mg of prednisone daily for one month or longer, a threshold our patient did not meet. This is a unique case of PCP in an immunocompetent patient where diagnosis was delayed due to lack of typical risk factors. We recommend testing for PCP early, even in patients without classic risk factors, if there is clinical suspicion for infection
-
Pharmacist impact on the time to post-intubation sedation in the Emergency Department
Brent Inouye, BS, PharmD; Paul VanEmmerik, PharmD; and Savita Bathija, PharmD
Abstract: Providence Portland Medical Center (PPMC) is a 483-bed community teaching hospital with approximately 50,600 annual emergency department (ED) visits and an average of 150 ED visits per day. Rapid sequence intubation (RSI) is an airway management technique that is commonly performed in the ED and involves administration of an induction agent followed by a neuromuscular blocking agent (NMBA). Emerging evidence suggests that approximately 2.6% of patients who undergo RSI in the ED experience awareness with paralysis (AWP), a devastating recollection of sensory perceptions while under the influence of a NMBA. Given the significant psychological sequalae associated with AWP, timely post-intubation sedation is essential. PPMC’s current staffing model has an ED pharmacist available daily between the hours of 1200 and 2230. While on duty, the ED pharmacist is responsible for medication management during the RSI procedure, as well as the management of post intubation sedation. The objective of this study is to evaluate the impact of having an ED pharmacist at the bedside during an RSI procedure on the time to initiation of post-intubation sedation in the ED. This is an IRB-approved retrospective cohort study of adults 18 years of age or older who presented to the PPMC ED between January 1, 2020 and October 31, 2024 and received a dose of either rocuronium or vecuronium in the ED for RSI. The primary outcome is the mean time to post-intubation sedation following RSI in the ED, with and without an ED pharmacist present at bedside. Key secondary outcomes include frequency of post-intubation sedation, time to and frequency of adequate post-intubation sedation, ED length of stay, and mean doses of RSI and sedative medications. Overall, 196 patients were included in the analysis. There were 107 patients who underwent RSI with an ED pharmacist present, and 89 patients with an ED pharmacist absent. Both cohorts had similar baseline characteristics. The mean time to sedation was 12 minutes with an ED pharmacist present and 20 minutes with an ED pharmacist absent (p = 0.009). When an ED pharmacist was present compared to when an ED pharmacist was absent, patients more frequently re-ceived post-intubation sedation (90.7% vs 87.8%), more frequently received adequate post-intubation sedation (75.9% vs 62.9%), and had faster mean times to adequate sedation (20 minutes vs 39 minutes). There were no significant differences between mean doses of RSI medications aside from the pharmacist present group receiving a higher mean cumulative propofol dose (3148.6 mcg/kg vs 2004.0 mcg/kg). ED LOS was not significantly different between groups. In conclusion, a bedside ED pharmacist assisting with medication management during RSI procedures significantly decreased the time to the provision of post-intubation sedation. Patients were also more likely to receive post-intubation sedation in the ED and achieved a higher frequency of adequate sedation.
-
Case Study: A Severe Presentation of Chronic Eosinophilic Pneumonia.
Revati Kalluri and Mari Kai
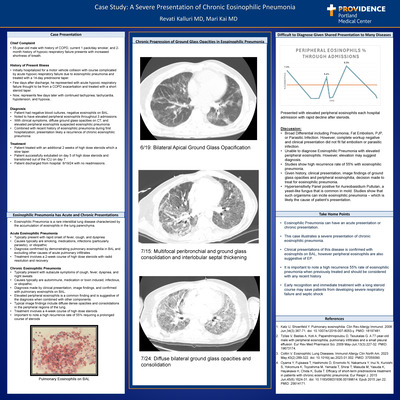
Case Presentation: Chief Complaint •55-year-old male with history of COPD, current 1 pack/day smoker, and 2-month history of hypoxic respiratory failure presents with increased shortness of breath. History of Present Illness •Initially hospitalized for a motor vehicle collision with course complicated by acute hypoxic respiratory failure due to eosinophilic pneumonia and treated with a 14-day prednisone taper. •Few days after discharge, he represented with acute hypoxic respiratory failure thought to be from a COPD exacerbation and treated with a short steroid taper. •Now, represents few days later with continued tachypnea, tachycardia, hypotension, and hypoxia.. Discussion: •Broad Differential including Pneumonia, Fat Embolism, PJP, or Parasitic Infection. However, complete workup negative and clinical presentation did not fit fat embolism or parasitic infection. •Unable to diagnose Eosinophilic Pneumonia with elevated peripheral eosinophils. However, elevation may suggest diagnosis. •Studies show high recurrence rate of 55% with eosinophilic pneumonia. •Given history, clinical presentation, image findings of ground glass opacities and peripheral eosinophilia, decision made to treat for eosinophilic pneumonia. Hypersensitivity Panel positive for Aureobasidium Pullulan, a yeast-like fungus that is common in mold. Studies show that such organisms can incite eosinophilic pneumonia – which is likely the cause of patient’s presentation Take Home Points; •Eosinophilic Pneumonia can have an acute presentation or chronic presentation. •This case illustrates a severe presentation of chronic eosinophilic pneumonia. •Clinical presentations of this disease is confirmed with eosinophils on BAL, however peripheral eosinophils are also suggestive of EP. •It is important to note a high recurrence 55% rate of eosinophilic pneumonia when previously treated and should be considered with any recent history. •Early recognition and immediate treatment with a long steroid course may save patients from developing severe respiratory failure and septic shock
-

From Dormant to Dangerous: Hepatitis B Reactivation Under Immunosuppression
Adam Knott, MD and Amy Dechet
Introduction: •HBV reactivation is a known phenomenon affecting those with prior HBV infection. In rare cases, this occurs spontaneously, but most often reactivation will occur while the host is immunocompromised. •Hepatitis B Virus (HBV) remains in the nucleus of hepatocytes and cannot be fully eradicated. •The following case highlights important considerations regarding HBV. Case Presentation: •A 78 y.o. male presented with emesis and progressive painless jaundice. •Prior history of treated HCV, Hepatocellular Carcinoma, HBV vaccination, and autoimmune Interstitial Lung Disease on Mycophenolate. •No recent risk factors, such as alcohol use, IV drug use, or sexual activity. •Previous tests for Hepatitis B Surface Antibody (HBsAb) were positive and negative for Hepatitis B Surface Antigen (HBsAg) in 2015. Learning Points: •This case demonstrates multiple important lessons: at risk.First, it’s important to recognize the risk factors that place pa tients at risk for decompensation. Second, initiating immunosuppression necessitates appropriate screen ing and risk stratification. Third, Hepatitis B Core Antibody (HBcAb) testing should be performed to look for prior infection as testing for HBsAg and HBsAb alone is insufficient in those
-
Developing a Hospital Medicine Elective for a Family Medicine Residency
Alissa Kummer and Justin Osborn
Background: Inpatient medicine is a key area of family medicine training, providing experiences in both triage and management of decompensated illness and building skills in safe transitions back to outpatient care. There is a growing trend of FM-trained physicians providing inpatient care (3-7% growth in some studies), but the training in many FM programs lacks the volume of hospital medicine that is needed for comfort with independent hospital work. Despite our FM residency including more hospital medicine training than many FM programs, and more than required of FM residencies per ACGME guidelines, there were still deficits in our volume of inpatient day coverage and critical care training when compared to two local IM residencies. Purpose: We aimed to design a hospital medicine elective experience that FM residents could take in the PGY2 or PGY3 years to augment the inpatient medicine experiences and help residents gain further proficiency in acute and critical patient care. Design: The elective was designed as a 4-week experience. The residents taking any elective rotations were surveyed in July of the 2024-2025 academic year, and again in February. Setting & Participants: Participants were PGY3 family medicine residents at a small, academic community hospital. Intervention: The 4-week elective implemented during the 2024-2025 academic year included 2 weeks of critical care time, a one-week rotation with a community hospitalist training residents to manage a higher volume of hospitalized patients, and one week focused on training in hospital-based procedures and POCUS. Main outcome measures: Residents evaluated their level of confidence with management of critical care cases, a high hospital census, and selected hospital procedures and POCUS skills at the beginning of the 2024-2025 academic year and in February 2025. Residents taking the hospital medicine elective also completed qualitative evaluations on the elective experience. Results: While the N of this study is underpowered for meaningful quantitative analysis (only two PGY3 residents chose to take this elective in the 2024-2025 academic year), key stakeholder interviews show success with POCUS training in the ED with 1:1 precepting, working directly with hospitalists, and gaining intubation experience with anesthesia providers. Areas for improvement included the ability to rotate at larger medical centers for medical ICU training, timing of hospital rotations to be during high-census seasons, and improvement in procedure training opportunities. Administrative staff gave feedback that the rotation was challenging to schedule given many preceptors and locations. Conclusions: Key learning points in the development of this elective were the challenges of coordinating complex elective experiences with multiple subspecialty partners and ensuring that residents are having high-value learning experiences. Key lessons from the post-elective stakeholder interviews include a need for a simplified schedule structure, improved procedural and ICU experiences, and ensuring residents can rotate in high hospital census seasons (although, this is unpredictable). Next steps are to discuss options for ICU and procedural experiences with program administration and work to develop ties with high-value learning opportunities.
-

A Diagnostic Challenge—TINU Syndrome
Sophia Lee, MD and Claire Kassakian, MD
Introduction: •TINU Syndrome: Tubulointerstitial Nephritis and Uveitis rare multi-system syndrome has renal manifestations typical of acute interstitial nephritis (AIN), in addition to bilateral anterior uveitis not well-understood •Thought to be an immune-mediated process, although mechanisms for disease remain unclear Likely secondary to a combination of genetic predisposition and certain environmental exposures •Genetic predisposition: specific HLA phenotypes possibly an auto-antigen to modified C-reactive protein (mCRP) •Potential triggers: Infections: tuberculosis, EBV, varicella zoster, chlamydia, toxoplasma Medications: antibiotics (β-lactams, meropenem, azithromycin, levofloxacin), NSAIDs, goreisan (Chinese herb) Endocrine diseases: hypoparathyroidism, hyperparathyroidism, rheumatoid arthritis, IgG4-related autoimmune disease, thrombotic microangiopathy Discussion & Learning Posts: •This case is an example of an extremely rare condition with potentially devastating outcomes if not caught early enough visual impairment dialysis dependence •Treatment for patients with progressive renal dysfunction is usually high-dose prednisone of 1 mg/kg per day (up to 40-60 mg/day) 3-6 month duration of treatment (depending on response) Long taper •Rarely, some patients are treated with mycophenolate mofetil if no benefit from steroid therapy •Fortunately, kidney disease can be self-limited in many patients, however, patients who have developed TINU syndrome are at risk of relapses •Demonstrates the need for a high clinical suspicion for this combination of symptoms: a pyuria suspicious for AIN tubular proteinuria eye redness and pain •Symptoms often do not correlate temporally! In fact, the majority of cases present with renal injury preceding uveitis •important to include TINU in the differential thoroughly assess a review of all systems when taking a history •Also key to note is the risk of future recurrence in patients who have developed TINU syndrome Need for ongoing monitoring
-
Adherence to Newer Lipid Guidelines
Shannon B. Leighton, PharmD; Giselle Sharifi, PharmD; and Diana Fischer, PharmD
Abstract: The American College of Cardiology (ACC)/American Heart Association (AHA) 2018 cholesterol guidelines provided recommendations for lipid lowering therapy in patients with clinical atherosclerotic cardiovascular disease (ASCVD) and very high risk ASCVD. The guidelines recommended reducing low-density lipoprotein cholesterol (LDL-C) by > 50% in patients with clinical ASCVD, however, there was little guidance for tar-geting a specific LDL-C measurement. Since the ACC/AHA 2018 cholesterol guidelines were published, newer guidelines, with more aggressive LDL-C targets have been published – specifically, the European Society of Cardiology (ESC)/European Atherosclerosis Society (EAS) 2019 Dyslipidemia guidelines and ESC 2021 Cardiovascular (CV) Disease Prevention guidelines. These updates further identify patients who should be considered for tighter LDL-C target goals. Patients identified with clinical ASCVD and very high risk ASCVD should have a target LDL-C < 55 mg/dL. Additionally, patients with > 2 CV events within 2 years of max tolerated statin therapy should have an LDL-C target < 40 mg/dL. Patient’s at very high risk ASCVD are defined as follows: • Severe CKD (eGFR < 30 mL/min/1.73 m2 or eGFR 30-44 mL/min/1.73 m2 and albu-min-to-creatinine ratio (ACR) > 30) • Patients with type 1 or type 2 diabetes mellitus with established ASCVD and/or severe target organ damage: eGFR < 45 mL/min/1.73 m2 irrespective of albuminuria eGFR 45-59 mL/min/1.73 m2 and microalbuminuria (ACR 30-300 mg/g) Proteinuria (ACR > 300 ng/g) Presence of microvascular disease in at least 3 different sites (e.g., microal-buminuria + retinopathy + neuropathy) • Patients with established ASCVD: Documented ASCVD, clinical or unequivocal im-aging. Documented clinical ASCVD includes previous AMI, ACS, coronary revas-cularization and other arterial revascularization procedures, stroke and TIA, aortic aneurysm and PAD. Unequivocal documented ASCVD on imaging includes plaque on coronary angiography or carotid ultrasound or on CTA. • SCORE2 or SCORE2-OP CVD risk score < 50 years old and score > 7.5% 50-69 years old and score > 10% > 70 years old and score > 15% Providers have received various education(s) throughout the years via continuing education, ACC/AHA and EAS/ESC communications, in-house service, etc. regarding lipid lowering therapy. Anecdotally, it seems that most providers are still practicing according to the ACC/AHA 2018 cholesterol guidelines. The purpose of this project is to assess and identify gaps in current clinical practice regarding lipid lowering therapy. Eventually, we may develop a stepwise approach for lipid lowering therapy.
-
Evaluation of Rapid Induction Using Extended-release Buprenorphine in Hospitalized Patients with Opioid Use Disorder
Bowei Liu PharmD; Nyles T Fowler; Jessica Dizon-Scheer, PharmD, MHA, BCPS; and Duyen-Anh Pham, PharmD
Abstract: Buprenorphine’s efficacy in treating opioid use disorder (OUD) is well established, markedly reducing opioid use, withdrawal symptoms, and mortality. Nevertheless, traditional sublingual (SL) induction protocols can be protracted and prone to nonadherence, thereby increasing length of hospitalization and healthcare costs. Extended-release buprenorphine (XR-BUP), formulated as a once-monthly subcutaneous injection (marketed as Sublocade® and Brixadi®), maintains consistent plasma concentrations, potentially enhancing adherence and reducing misuse compared to daily formulations. Studies suggest XR-BUP confers higher treatment retention, fewer positive urine drug screens, and improved patient-reported outcomes, including reduced cravings and withdrawal symptoms. In this retrospective cohort study, we sought to evaluate whether rapid inpatient XR-BUP induction decreases hospital length of stay (LOS), 90-day readmission rates relative to SL-BUP, continued opioid use, overdose events, and treatment retention compared to SL-BUP. Data was collected at a tertiary care center in two phases: a pre-implementation SL-BUP cohort (n=26) from January to June 2024, and a post-implementation XR-BUP cohort (n=11) from August 2024 to February 2025. The primary endpoint was LOS, analyzed using two-sample t-tests, while secondary endpoints included readmissions at 30 and 90 days, continued opioid use, and overdose incidence, assessed via chi-square tests and logistic regression. The preliminary results presented a mean LOS of 11.04 days for the SL-BUP group and 5.82 days for the XR-BUP group, suggesting a trend toward shorter LOS in the XR-BUP group. Readmission rates at 90 days were 46.2% (12/26) in the SL-BUP group versus 30.0% (3/10) in the XR-BUP group; logistic regression yielded an odds ratio (OR) of 0.50 (95% CI: 0.30–0.85; p=0.013) in favor of XR-BUP, signifying a 50% decrease in the odds of unplanned readmission. Furthermore, patients receiving XR-BUP had significantly lower odds of continued opioid use (OR 0.33; 95% CI: 0.19–0.57), but overdose events did not differ significantly between groups (OR 1.49; 95% CI: 0.80–2.78; p=0.20). Notably, those who continued to use opioids after discharge were more likely to experience subsequent readmissions, underscoring the potential benefit of strategies that curtail ongoing opioid use. The preliminary results collectively suggest that early administration of XR-BUP could shorten hospital stays, lower readmission rates, and reduce continued opioid use among hospitalized OUD patients. Additional patient enrollment through August 2025 is underway to bolster the dataset and increase statistical power, with final determinations to be made upon completion of the data collection period. A comprehensive cost-effectiveness analysis will also be performed to ascertain whether XR-BUP’s higher acquisition cost is offset by healthcare savings associated with fewer readmissions and shorter length of stay. This study is approved by the Institutional Review Board. Learning Objectives: Evaluate whether initiating XR-BUP during hospitalization reduces length of stay, readmission rates, continued opioid use, overdose incidence, and improves treatment retention compared to traditional SL-BUP induction. Presentation Category: Inpatient Clinical Services
-
Evaluation of Implementation of a Clinical Pharmacist in Outpatient Cardiology Services
Katherine Lyon, PharmD; Kristin A. Tallman, PharmD, MS, BCPS, BCACP; and Susie Fedler
Abstract: Incorporation of clinical pharmacists in chronic disease medication management in primary care clinics has been well-established by the literature to improve patient outcomes. Limited information is available regarding the proper model to integrate a clinical pharmacy specialist (CPS) into a cardiology clinic and assess the impact on patient outcomes. Currently at Providence Medical Group (PMG), CPSs are well established and have been managing hypertension and lipid medications for patients in primary care clinics via a collaborative practice agreement (CPA). Now Providence has expanded its clinical pharmacy services to cardiology, however, the recent implementation of a CPS in the Providence Heart Clinic outpatient clinics at Providence has yet to be evaluated. The purpose of this clinical inquiry is to track pharmacist utilization and identify optimal CPS role within the cardiology clinic. This is a single institution retrospective chart review of patients 18 years or older who have been referred to clinical pharmacy from a cardiology provider at Providence Heart Clinic outpatient facilities in the Oregon region from September 2024 through March 2025. As part of the cardiology CPS workflow, various activities performed for the clinic/patients are documented via Epic iVents and Episodes of Care (EOC) as well as standard chart notes. IVents and EOCs will be reviewed to quantify and categorize clinical pharmacy services in the cardiology clinic and pharmacist utilization per month. Manual chart review will be performed as needed. The primary outcome will describe pharmacist utilization focusing on number of patients referred, breakdown in visit types (office vs telephone), indication for referral, and CPS time spent on various activities (appointments, consults, care coordination, population health). Secondary outcomes will evaluate the change in blood pressure, change in weight, and optimization of heart failure guideline-directed medical therapy after CPS intervention(s). Outcomes will be evaluated using descriptive statistical analyses. Results and conclusions will be shared when the project is completed. (IRB exempt) Learning Objectives: • Discuss the literature surrounding ambulatory care pharmacist integrated in cardiology clinics • Describe cardiology clinical pharmacy specialist utilization within cardiology clinics at Providence in the Oregon Region • Quantify the average change in BP, weight and GDMT regimen after CPS intervention(s) Presentation Category: Ambulatory Care/Disease State Management, Cardiology, Clinical Services Development
-
Improving Pediatric Fluoridation at Providence Southeast Family Medicine
Iman Malik, Brian Bizub, Andrew Tobler, and Ben Pederson
Dental caries are the most common preventable chronic condition effecting children worldwide. The patient population at Providence Southeast Family Medicine (PMG SE) are disproportionally affected by high caries rates due to lack of fluorinated water supply, low socioeconomic status, and limited access to pediatric dental services. Although application of topical fluoride is an effective strategy for prevention of caries, it is not routinely completed during office visits. PMG SE did not have an established workflow for fluoride application in clinic. We implemented a quality improvement (QI) project to increase the rate of fluoride application in children ages 6 months through 5 years old during Well Child Checks (WCCs) to a target of a 25% success rate. We completed a detailed root cause analysis and stakeholder interviews that informed the development of our QI project. Through a series of four Plan-Do-Study-Act (PDSA) cycles, we implemented a new clinical workflow to improve process measures of 1) provider education, 2) identifying eligible patients, 3) provider and medical assistant reminders through chart scrubbing, and 4) providing parent education. We achieved our target of successfully applying fluoride for 25% of WCCs after PDSA #1 and sustained a success rate of greater than 40% by the end of completion of PDSA #4. This project demonstrates the impact and success of implementing a simple workflow within the outpatient clinical setting to improve dental health for our at-risk patient population.
-
Impact of probiotics on a incidence of necrotizing enterocolitis in premature neonates in a level III NICU within a community hospital
Connor Manning, PharmD; Aiyana Ooki-Knutson; and Erin Wilson
Abstract: Necrotizing enterocolitis (NEC) is a serious intestinal condition in neonates associated with significant morbidity and mortality. Evidence supporting the use of probiotics for prevention of NEC has prompted use among neonatal intensive care units (NICU) throughout the United States. In 2023, a case involving the death of a neonate with sepsis attributed to Bifidobacterium led to the FDA releasing multiple statements warning against the use of probiotics in neonates. The purpose of this study is to evaluate the efficacy and safety of probiotics in the prevention of NEC. This is a retrospective cohort study of patients admitted to the NICU from November 1, 2022 to August 31, 2023 and from November 1, 2023 to August 31, 2024. Data was collected utilizing chart review in an electronic medical record. The probiotic cohort is defined as patients admitted between November 1, 2022 and August 31, 2023, and the non-probiotic cohort is defined as patients admitted between November 1, 2023 and August 31, 2023. The primary outcome is the rate of NEC during hospital admission. Secondary outcomes include incidence of late onset sepsis, survival to discharge, and time to full enteral feeds. Investigators obtained institutional review board approval prior to data collection. After data collection, 63 patients were included in the probiotic cohort, and 64 patients were included in the non-probiotic cohort. Four patients developed NEC during admission; 1 from the probiotic group, and 3 from the non-probiotic group (p>0.30). Differences in rates of sepsis were not significant (p>0.80). Survival to discharge showed negligible difference between the two groups. Mann-Whitney test showed no difference for the endpoint to full enteral feeds (p>0.95). This study saw no difference in outcomes between probiotic and non-probiotic cohorts. Learning objective: Understand the hypothesized mechanism of action for probiotics in NEC. Discuss evidence for and against the use of probiotics to prevent NEC. Presentation Category: Pediatrics
-
Characterization of Institution-Specific Risk Factors for Post-Operative Atrial Fibrillation in Patients Undergoing Cardiac Surgery
Ruth Murar, PharmD; Sarah Bailou, PharmD, MPH, BCCCP; Emily H. Hsu; and Gideon Berdahl, PharmD, BCCCP
Abstract: Postoperative atrial fibrillation (POAF) is a common complication following cardiac surgery and is associated with increased morbidity, prolonged hospitalization, and higher healthcare costs. Risk assessment tools have attempted to predict POAF using factors such as comorbidities, cardiac function, and perioperative characteristics, but these variables have not been consistently validated or standardized across diverse patient populations. This retrospective, single-center study aimed to characterize the proposed clinical and perioperative POAF risk factors in patients undergoing coronary artery bypass grafting (CABG), aortic valve replacement (AVR), mitral valve replacement (MVR), or a combination of these procedures at Providence St. Vincent Medical Center between July 30, 2022, and September 2, 2024. Following IRB approval in December 2024, 1,287 patients were screened using the Adult Cardiac Surgery Database; of these, 951 met inclusion criteria and were stratified into two groups: those who developed POAF after 48 hours post-procedure and those who did not. Comparative analyses were conducted using Wilcoxon rank-sum, chi-square, and T-tests. Patient characteristics studied include age, gender, comorbidities (e.g., hypertension, COPD, diabetes), procedure characteristics, and relevant periprocedural medications. Perioperative electrolyte levels (potassium and magnesium) were also collected via Epic’s SlicerDicer tool and manual chart review. Analysis of potassium and magnesium trends are ongoing to evaluate their potential predictive value. Results indicated that POAF was more common among patients undergoing complex procedures, particularly combination surgeries including AVR + CABG (9.21% POAF vs. 7.42% non-POAF, p < 0.000001), MVR + CABG (2.3% POAF vs. 0.31% non-POAF, p < 0.000001), as well as isolated MVR (3.95% POAF vs. 2.47% non-POAF). In contrast, isolated CABG (39.1% POAF vs. 51.3% non-POAF, p < 0.000001) and AVR (12.17% POAF vs. 15.3% non-POAF, p 0.000001) were associated with lower POAF incidence, suggest-ing that procedure type and additive effects of combination surgery significantly impacts arrhythmia risk. While many baseline characteristics were similar be-tween groups, POAF was more frequent in patients with COPD (22% POAF vs 17% non-POAF, p < 0.05), prior cerebrovascular accidents (10.86% POAF vs. 6.34% non-POAF, p < 0.02), and history of myocardial infarction occurring 21 days or later prior to surgery (13.82% POAF vs 10.97% non-POAF, p < 0.05). Additionally, postoperative serum creatinine 48 hours post-surgery was statistically significantly higher in the POAF group (p < 0.004), indicating an association with renal dysfunction. These findings are consistent with prior research linking procedural complexity and cardiopulmonary comorbidities to POAF, though the stronger associations seen with combination valve procedures and renal dysfunction are less well described in the literature.
-
Mycotic Aneurysm and Rare Complication from Infection Masquerading as Lung Cancer
Rithvik Nallapareddy and Mary Anne Nidiry
Introduction: Mycotic Aneurysm: Dilation of an arterial wall due to infection • Majority are bacterial, Staphylococcus and Salmonella • Called mycotic because it resembled the appearance of fleshy fungus1 • Most commonly in femoral artery, aorta, and visceral Causes • Form from adjacent bacteria infections • Lung, esophagus, endocarditis • Direct invasion of vessel walls or atherosclerotic plaque in bacteremia General Presentation • Fever, back pain, immunocompromised, IV drug user • Positive blood cultures 50-85%2 • Elevated WBC, ESR, CRP • Lack of standard criteria for diagnosis and management Risk Factors • Tobacco • Atherosclerosis • Diabetes Mellitus Case Presentation: • A 74 year old male presents with worsening fevers and generalized body pains over the last three weeks. In addition he endorsed weight loss, chills, sweats, generalized body aches, and hoarseness of voice • Patient had a above knee amputation 5 weeks ago and he started to have fevers and was started on Augmentin. • Wound cultures at this time grew Staph aureus and enterococcus faecalis. • Started on ceftriaxone and vancomycin outpatient • Incidentally during history on admission patient mentions blood streaks in mucus when patient coughs for the last few days • Blood culture: Positive for methicillin sensitive staph aures Discussion: Would we approach a similar patient in the future differently? • The lack of clear diagnostic criteria other than imaging makes this difficult to diagnose. • Should the initial CT have been one with contrast? Inflammation around a vessel can look like a mass around a vessel. • You cannot diagnose patient with lung cancer until the results of pathology come back. • A primary lung nodule if found incidentally on CT many years ago likely did not become lung cancer This case shows a rare complication from an infection that requires complex and urgent medical management that can present in an incidental manner • Really difficult to predict manifestation of infection or sepsis around the body.
-
Raise the Rates: Improving Influenza Vaccination Rates at PMG NE Clinic
Tho Nguyen, MD
Background: At Providence Medical Group at Northeast Clinic (PMG-NE), the rate of influenza vaccination was lower in year 2022-2023 compared to three years prior. An EPIC database query from 2019-2022 revealed average rate of 47% patients vaccinated with the flu compared to rate of 37% in 2022-2023. This quality improvement project aimed to improve the vaccination rate to 50% for year 2023-2024. Setting and Population: Providence Medical Group – Northeast Clinic Project Description: The primary part of the workflow was having front desk staff ask patient whether patient was interested in getting the influenza vaccine. If the patient indicated yes, *FLU* was put in the appointment note. The idea was to make rooming more efficient and allow medical assistants to utilize standing orders faster. In addition, regardless of whether *FLU* was put in the appt note, the medical assistant was supposed to ask every patient about flu vaccination to ensure that every patient gets asked at least twice during the visit. Lastly, all providers get a weekly email re-minder to look at the EMR alert in every patient’s chart about vaccination so they can address with their patient. Results: Influenza vaccination rate for year 2023-2024 was 34% with a total of 497 patients vaccinated. Lesson Learned: Immunization is a team effort, and it is clear from this quality improvement project that everybody plays a critical role in vaccinating patients.
-
The impact of an emergency department code sepsis alert on empiric antibiotic effectiveness
Elizabeth Nguyen, PharmD; Samantha Wagner, PharmD, BCEMP; and Sarah Ballou, PharmD, MPH, BCCCP
Abstract: Sepsis bundles, known as SEP-1, provide hourly recommendations to ensure timely identification and administration of antibiotics to patients with sepsis or septic shock. To ensure compliance with SEP-1, the Centers for Medicare and Medicaid Services (CMS) tied hospital reimbursements to SEP-1 protocol adherence in early 2024. Since these reimbursements have been put in place, there have been limited studies to evaluate antibiotic prescribing practices. This study aims to evaluate the impact of a Code Sepsis alert on empiric antibiotic prescribing practices for patients with sepsis or septic shock in the Emergency Department at Providence St. Vincent Medical Center (PSVMC). This is a single-center, retrospective chart review study including adult patients > 18 years old who met CMS sepsis criteria and received antibiotics in the Emergency Department (ED) from February 2023 to May 2024. This study utilizes the Providence Acute Care Sepsis Matrix Explorer, an existing data set for patients who qualify for sepsis diagnoses based off CMS sepsis criteria in the ED at PSVMC. The primary outcome is an assessment of the effectiveness of the empiric antibiotic(s) prescribed for patients meeting sepsis criteria in the ED before and after a Code Sepsis alert implementation. Effectiveness will be assessed by using culture data to evaluate antibiotic coverage and discharge diagnoses to determine if patients had true infections. Secondary outcomes include SEP-1 compliance (time to antibiotic administration < 60 minutes), inpatient mortality, and changes in prescribing patterns using the antibiotic spectrum index (ASI) score. Baseline characteristics will be evaluated using descriptive statistics. Chi-squares tests will be used to evaluate the primary and secondary outcomes. The effects of multifactorial variables (lactate value, vasopressor use, duration of septic shock, and number of hypotensive episodes) on survivorship at 24 and 72 hours will be evaluated using linear binomial regression. A two-tailed significance of p < 0.05 will be considered statistically significant. Preliminary results will be presented, and conclusions will be presented when the project is completed (IRB approved). Learning Objectives: Evaluate the impact of a code sepsis alert on empiric antibiotic effectiveness for patients with sepsis or septic shock. Presentation Category: Emergency Department
Printing is not supported at the primary Gallery Thumbnail page. Please first navigate to a specific Image before printing.