-

IVIG Stewardship to Evaluate Outpatient Infusion Use
Judy Nguyen, PharmD and Ian Ingram
Abstract: IVIG is an IV medicine that is made from human donor plasma and is approved to treat low Immunoglobulin G (IgG) serum levels to reduce the risk of infections. IgG is the most common antibody and is a part of the immune system to help protect against bacterial and viral infections. IVIG works by modulating cells in the immune system to help replenish low IgG levels. Current CDC and NCCN guidelines recommend IVIG replacement for IgG levels < 500 mg/dL for hypogammaglobulinemia caused by different disease states such as CLL, multiple myeloma, B-cell malignancies. Based on current observations and practices at Providence Franz Cancer Center, IVIG is administered at regular intervals without regard to IgG levels. With anticipation of increased use of IVIG with recent approval of multiple bispecific antibodies that recommend using IVIG prophylaxis, a more formal use criteria protocol for IVIG is necessary to assure appropriate use and avoid unnecessary treatment and cost for patients. Eligible patients ≥18 years old who received IVIG between January 2023 to January 2025 at Providence Franz Cancer Center and Providence Outpatient Infusion Center. Patients with hypogammaglobulinemia, CLL, multiple myeloma, immunodeficiency, follicular lymphoma, diffuse large B-cell lymphoma. Data collection through SlicerDicer with IVIG administration from January 2023 to January 2025 and manual chart review to obtain dose and frequency of IVIG and IgG levels as available. Project evaluates use of IVIG and compliance with IgG level-based dosing to identify if administration is appropriate based on current recommendations. The aim of the project is to evaluate overall IVIG use, and patients’ cost savings and treatment burden associated with IgG level-based dosing. Preliminary results will be presented. Results and conclusions will be shared when the project is completed. (IRB exempt).
-
Building Climate Resilience in Primary Care by Preparing Patients for Extreme Heat
Tiffany Nguyen
Background • Extreme heat is the leading cause of weather-related deaths in the US and extreme heat events are projected to become more frequent and severe with climate change. • Extreme heat can lead to illness or death through exacerbation of chronic illnesses. • Populations at higher risk include older adults, pregnant patients, young children, and those with chronic medical conditions such as cardiovascular disease, lung conditions, substance use, chronic kidney disease, mental health conditions. • It also disproportionately affects marginalized residents and those who face systemic inequities • Access to air conditioning (AC) is a life-saving intervention for preventing heat-related illness and mortality. • Community initiatives, such as the Cooling Portland program, were developed to connect low-income Portland residents with cooling devices. Some insurance plans, such as the Oregon Health Plan, also have a climate benefit that provides coverage of climate devices. However, not all patients are aware of these programs. • Primary care clinics are uniquely positioned to assess patients who are at increased risk for heat-related illness, provide education on safety interventions, and bring awareness about programs offering climate resources. Objectives • Primary Objective: Identify patients with increased risk of heat-related illness to screen for access to air conditioning and offer additional patient information for staying safe during extreme heat. • Secondary Objective: Identify the most effective approach for outreach to high-risk patients. Methods • Epic SlicerDicer was used to help identify patients on my panel who had a medical condition that increased their risk of heat-related illness. The risk factors used in-clude: age over 65 years, history of asthma or COPD, history of CHF, history of CAD, history of substance use disorder. • Data collection: I directly performed outreach to all patients with risk factors either through office visit or phone call throughout the months of February and March in order to provide adequate time to apply and receive an AC device prior to the sum-mer. • During each encounter, patients were screened by asking if they had a working air conditioner and if they wanted additional resources. • Patients who did not have access to AC were then connected to the clinic care coordinator who provided information on which program they would be eligible for based on health insurance. Results • Out of the patients on my panel who had risk factors for heat-related illness, 46% were able to be contacted to screen for access to AC (24.3% during an office visit, 75.7% contacted by phone call). • Out of the patients who were screened, 13.5% reported not having access to AC and 29.7% requested to have additional information about resources sent to them.
-
Evaluating the role of social determinants of health on disparities in breast and prostate cancer screening and treatment: a retrospective analysis
Zach Nunemaker, PharmD and Jenifer Smith
Recent advances in cancer screening and treatment have led to improved outcomes, including earlier detection, increased overall survival rates, and enhanced quality of life across several cancer types. Despite these advancements, significant disparities in cancer care persist across the United States, particularly among racial and ethnic minority groups and medically underserved populations. These disparities are largely driven by the complex interplay of social determinants of health (SDOH). Although extensive research has been conducted, substantial knowledge gaps remain in understanding how SDOH contribute to disparities in cancer screening and treatment, specifically for breast and prostate cancer. The purpose of this study is to evaluate whether an association exists between key SDOH (such as socioeconomic status, race/ethnicity, language, geographic location) and outcomes for patients diagnosed with breast or prostate cancer. Additionally, we assessed whether these factors contribute to delayed diagnoses and higher rates of late-stage cancer at presentation. Findings from this study will help inform targeted interventions and policies aimed at reducing disparities and improving outcomes for all individuals across the cancer care continuum. This is a single center retrospective cohort analysis of Providence Health Plan (PHP) patients diagnosed with breast or prostate cancer between January 1, 2022 and December 31, 2024. Patients for all lines of business (Commercial, Medicare, and Medicaid) with continuous enrollment in health plan (six years prior to breast cancer diagnosis and 10 years prior to prostate cancer diagnosis) and within screening recommendation age group (≤70 years for prostate cancer and females ≤75 years for breast cancer) were included. The primary outcome is to determine whether SDOH are associated with lower rates of receiving guideline-recommended screening and/or first-line treatment. The secondary outcome is to determine whether SDOH are associated with worse clinical outcome, defined as late-stage disease at time of diagnosis. Results and conclusions will be shared upon completion of the project. This study is IRB exempt. Learning objectives: 1. Identify the social determinants of health that contribute to disparities in breast and prostate cancer screening and treatment 2. Discuss the implications of screening and treatment disparities related to social determinants of health on cancer stage at diagnosis in patients with breast and prostate cancer Presentation Category: Managed Care/Population Health
-
Walking the Razor’s Edge: A Crossover Between Infection and Malignancy
Brenna Ostertag, MD and Gita D Gelfer
Background: . • Lyme disease is a multisystem infection caused by the spirochete species Borrelia. The most common subspecies seen in the United States is Borrelia Burgdorferi6-7 • 10-15% of infections seen in the United States have neurologic involvement, known as neuroborreliosis4 • Presenting symptoms often include unilateral or bilateral facial nerve palsy, but patients may also have focal weakness and/or polyradiculitis4, 6-7 • Lumbar puncture in neuroborreliosis demonstrates lymphocytic pleocytosis • The above combination of neurologic and diagnostic findings are also seen in presentations of primary or secondary CNS lymphoma10, 12- Case Presentation: • 62-year-old woman with a history of POT1 mutation presents with 3 weeks of increasing neurologic symptoms including headache, bilateral CN VII palsies, and now focal weakness and paresthesias • Symptoms started after a road trip back to Oregon from the East coast where she had been camping during the summer • Initially presented with unilateral CN VII palsy and arm pain • She had been hospitalized two times in the last two weeks related to symp-toms without any conclusive explanation Physical Exam Findings • Bilateral CN VII palsies leading to inability to close either eye fully, move mouth normally • Focal weakness in proximal L arm, proximal L leg • Paresthesias in dermatomal distributions including T10, L2, L3 that were painful when elicited by palpation Hospital Course • Imaging and lumbar puncture completed which showed atypical lymphocytes • Started on empiric antibiotic therapy with ceftriaxone • Flow cytometry concerning for B cell lymphoma, however Lyme antibody titers returned positive in CSF • Patient declined any treatment for lymphoma, neurologic symptoms slowly improved with antibiotics alone • Discharged with close oncology and infectious disease follow-up
-
Safety of Linezolid Administration in Patients Receiving Serotonergic Medications
Nyda Ouch, Emily Fox, Greg Tallman, and David Chen
Background: Linezolid is an oxazolidinone antibiotic with activity against gram positive organisms, including methicillin-resistant Staphylococcus aureus (MRSA). However, the use of linezolid has been limited due to concerns for drug interactions and the risk of precipitating serotonin syndrome. There is a growing body of retrospective evidence that suggests that the risk of serotonin syndrome in patients receiving linezolid and serotonergic agents is extremely rare. This study will assess the incidence of serotonin syndrome in hospitalized patients receiving linezolid with or without a concomitant serotonergic agent. Methods: This is a multicenter, retrospective cohort study of patients hospitalized at one of the eight hospitals within Providence St Joseph Health System in Oregon between January to October 2023. Patients were included if they were at least 18 years of age and received linezolid during a hospital admission. The comparator groups were patients receiving linezolid monotherapy and patients receiving at least one dose of a serotonergic agent within 24 hours of linezolid administration. The primary outcome was the incidence of serotonin syndrome. The secondary outcome will be in-hospital mortality. The presence of serotonin syndrome was determined by physician-diagnosed serotonin syndrome or was considered a likely diagnosis of serotonin syndrome using the Hunter criteria and Sternbach criteria. Electronic medical records were searched for terms related to the presence of serotonin syndrome including serotonin syndrome, clonus, myoclonus, tremor, hyperreflexia, hypertonic, agitation, shivering, incoordination, fever, diaphoresis, incoordination, and all results related to serotonin. Results: Research in progress, data analysis will be finalized in April 2024 (IRB approved).
-
Implementation and Assessment of a Novel Family Medicine Residency Geriatrics And Palliative Care Selective Curriculum
Mary Parker and Jessica Valls Burness
Background: Family medicine physicians are integral to delivering personalized care for elderly patients and those with severe illnesses, who often encounter high symptom burdens, challenging treatment decisions, and end-of-life circumstances. The Geriatrics and Palliative Care Selective at Providence Oregon Family Medicine Residency is de-signed to enhance resident expertise in geriatric care by immersing them in multidisci-plinary settings. Through a blend of ambulatory clinical visits, home visits, and facility engagements, residents provide comprehensive palliative and hospice care. Educational components include practical experiences supplemented by online modules, articles, and videos. Methods: The selective aims to build competencies in several areas: prescribing appro-priate medications considering age-related changes, managing end-of-life symptoms, utilizing screening tools for delirium, dementia, depression, and substance abuse, fos-tering evidence-based practices, improving shared decision-making and patient advoca-cy, promoting professionalism, and enhancing communication skills. Residents engage in home visits, clinic sessions, and nursing home rotations, supported by online educational resources, fostering practical skills in real-world settings. The hypothesis posited that participation in the selective would enhance residents' compe-tency assessments in geriatrics and palliative care. Assessment methods include pre and post surveys for residents and qualitative evaluations after rotations. Results: Results showed residents who participated in the selective reported higher self-reported competency levels in specific geriatrics and palliative care topics. Statistical analysis revealed a significant improvement in confidence, with those having complet-ed the selective scoring an average of 59.4 compared to 47.7 for non-participants, (p-value of 0.0004). Pre and post survey comparisons of all residents indicated improve-ment, with scores increasing from 40.6 to 53.6, (p-value 0.01). Discussion: While the study demonstrated increased comfort and competence in geriat-rics and palliative care for participants, limitations included small sample size, non-randomized groups, and reliance on subjective survey data. The study scored 6 out of 18 on the Medical Education Research Study Quality Instrument (MERSQI), impacted by incomplete response rates and lack of matched survey data. Despite these con-straints, the selective shows promise as a model for enhancing family medicine residen-cy programs' approach to geriatric and palliative care training. Future improvements involve refining assessment methodologies to incorporate objec-tive evaluations, increasing response rates, and integrating randomized sampling to enhance statistical analysis rigor. Addressing these challenges with further study may help us to improve the selective's cultivation of residents' skills navigating geriatric and palliative care complexities.
-
Evaluating the Effectiveness of an Addiction Medicine Selective to Increase Resident Confidence in Treating Patients with Substance use Disorder
Kristine Park and Tanya Page
Background: Substance use disorder is a growing problem across America. It is important that primary care physicians are well trained and comfortable treating these conditions. ACGME has also prioritized this area of resident learning and increased required elective time for residents. To create better educated doctors and follow guidelines placed by the ACGME, we developed a four-week curriculum, called the addiction medicine selective, to increase resident comfort and knowledge in diagnosing and treating patients with substance use disorders in multiple settings. Methods: Analyze the effectiveness of a four-week addiction medicine focused cur-riculum with an anonymous, categorical survey that was administered to all second- and third-year residents at the beginning and end of the 2024-2025 academic year. 7 out of 14 residents completed the addiction medicine selective during this academic year. The survey included a confidence scale from not confident, slightly confident, somewhat confident, fairly confident and completely confident/fully independent regarding specific topics in diagnosing and managing substance use disorders in an inpatient and outpatient setting. Results: 11 residents completed the pre selective survey and 14 completed the post selective survey. Overall, there was an average increase of 33% in those who felt fairly confident or higher in all topics related to treating opioid and alcohol use disorder. Knowledge around community resources for patients with substance use disorder had the smallest change in response with only a 14% increase to fairly confident or higher. For the residents who completed the selective, they were all slightly confident or higher in all topics. Only residents who took the selective felt they could independently diagnose alcohol and opioid use disorder. No resident felt completely confident in outpatient treatment of alcohol or opioid use disorder. Conclusion: There was an overall increase in residents who felt fairly confident or more in treating opioid and alcohol use disorders, which can be explained by the inherent nature of residency. However, there was a noticeable increase in confidence across all topics for those who completed the addiction medicine selective. In addition, more residents felt they could independently diagnose use disorder. In general, the selective did increase resident comfort and knowledge when caring for patients with substance use disorders. However, no residents felt completely confident in treating these conditions in an outpatient setting despite completing the selective. There are several factors that make outpatient management challenging for any health condition, but we will reach out to residents to get a better understanding of this difference compared to inpatient management. There was also a knowledge gap in community resources, which we are creating a dot phrase for so that this information is readily accessible to residents. Having an understanding of the available resources may also help to improve outpatient management. There were several limitations to this study, such as small sample size and the lack of consistent identifiers for the pre and post surveys. As a result, we were unable to analyze and correlate the improvement for an individual after completing the addiction medicine selective. This should be implemented for future surveys when analyzing the effectiveness of a curriculum
-
Ambulatory Pediatric Fluoridation
Kristine Park, Stephanie Rodriguez, Mary Parker, Alissa Kummer, and Daniel Ruegg
Context: Dental health is an important part of pediatric wellness. Early childhood caries represents the most common childhood chronic health condition. As such, dental health screening and intervention are crucial in primary care. Oral health disparities exist among children from low-income families, low family education status and Black and Hispanic children. These inequities are evidenced in a higher prevalence of cavities, lower treatment rates, and less access to preventative dental care. Fluoride varnish is a simple yet highly effective method of preventing dental decay in children- reducing the incidence of cavities by 30-50%. Americal Academy of Pediatrics recommends applying fluoride every 3-6 months until age 5 for all children, and every 3 months for high-risk children. USPFTF gives this a “B” recommendation. Goal: At PMG Milwaukie, there were 28 opportunities to apply fluoride varnish in September 2024. Only 4 patients received this treatment (14%). The goal of this project is to increase fluoride varnish rates during well child checks (WCC) for children ages 1-5 to 50% by March 31, 2025. Methods: Topical fluoride treatments during routine WCC for children ages 1 until age 6 were initiated through a workflow including clinic providers, medical assistants, and clinic leadership. In this workflow, the lead medical assistant will chart scrub and place the note “fluoride” in office visit notes. The rooming medical assistant will place a fluoride kit and toothbrush in the room, which also acts as a visual cue for the provider. The provider will educate the family on the importance of pediatric fluoride varnish, apply the fluoride varnish during the visit, and complete the billing, documentation, and after care instructions. For this project, the CPT code, documentation dot phrase, and after care instruction dot phrase were made clearly visible at each provider desk. Results: The baseline rate of pediatric fluoride varnish application in the clinic was 14%. PDSA cycles included following an idealized workflow, described above, provider reminders at individual desks including fluoridation coding instructions and dot phrases, a recommitment to the basic workflow after a downturn in rate of fluoridation around the holidays, and finally the most effective intervention; targeted reminders to providers seeing high numbers of children ages 1-5 resulting in a final fluoridation rate of 61%. Discussion: This project highlighted some of the challenges of implementing a new workflow in a busy primary care clinic in addition to obstacles in recommending new treatments and interventions to families. Barriers to providing higher rates of fluoride varnish at WCCs included providers remembering to discuss these recommendations, adequate time to focus on counseling around the importance of pediatric dental fluoride, and parents declining the service. Chart scrubs of the visit notes where fluoride was discussed but not applied highlighted the latter obstacle, as many possible varnish opportunities documented parental refusal. We noticed that the greatest improvement in rates of applying fluoride varnish came with focusing varnish application reminders on those providers in the clinic seeing the highest volume of pediatric patients. This finding also reinforces the small N number of this intervention. The overall goal of meeting a pediatric fluoride varnish application rate of 50% was met. Possible next steps include both improving high pediatric volume providers implementation of these recommendations and working long-term to address familial fluoride varnish hesitancy.
-

A Case of “Double Positive” Goodpasture Syndrome
Nidhi Patel, MD and Qian Leng, MD
Background: • Goodpasture Syndrome is a rare autoimmune vasculitis disorder that affects the glomerular capillaries, pulmonary capillaries, or both, with glomerular basement membrane (GBM)deposition of anti-GBM autoantibodies. • Initial presentationis generally characterized byrapidly progressive glomerulonephritisand diffuse alveolar hemorrhage • Early recognition and subsequent treatment are vital fof management of Goodpasture Case Presentation: • 59 F presenting to the ED with a month-long history of hemoptysis and shortness of breath • Had been living in her car and is a vague historian. Mentions previously traveling but would not specify where • Has had frequent nosebleeds and two new pruritic wounds on legs Discussion: • Anti-GBM disease or Goodpasture Syndrome is a rare disease that involves both the lungs and kidneys, often presenting as pulmonary hemorrhage and glomerulonephritis • ANCA positivity is associated with 20-30% of cases as a “double-positive” form of Goodpasture, with MPO being the more common form of ANCA positivity over PR3Double positive disease is at a higher risk of relapse in comparison to “pure” anti-GBM body disease • This case was unusual with PR3 positive ANCA antibody and treatment with rituximab instead of cyclophosphamide since the ANCA antibody resulted earlier than the anti-GBM antibody. • Early recognition is integral as it may reverse kidney damage and prevent the need for hemodialysis • Standard treatment for anti-GBM consists of corticosteroids, cyclophos-phamide, and plasmapheresisRituximab is used as a second line treatment if disease is refractory to cyclophosphamide • Rituximab may reduce antibody titers, but it does not consistently reverse dialysis dependency • Treatment for the diffuse alveolar hemorrhage requires pulse steroids for 3 days followed by a taper dose at 1 to 1.5 mg/kg/d. • “Double positive” patients require an aggressive early treatment for the anti-GBM disease phase, followed by careful long term follow up and potential immunosuppression for ANCA associated vasculitis phase • Patients also may opt to transition to comfort care, and it is important to consider their wishes when pursuing aggressive treatment
-
Efficacy of Procainamide vs Amiodarone for Atrial Fibrillation in Emergency Department Patients
Tommy Pham, PharmD; Emily H. Hsu; Marian Dobles; and Samantha Wagner, PharmD, BCEMP
Abstract: Procainamide has been shown to be safe and effective for atrial fibrillation, and it has a rapid onset to cardioversion. However, its efficacy compared to amiodarone is not well-characterized. Current literature suggests that procainamide may have a faster time to conversion than amiodarone. The purpose of this study is to compare rate and time to conversion of atrial fibrillation to normal sinus rhythm (NSR) between procainamide and amiodarone in emergency department (ED) patients. The potential to discharge patients more quickly and lessen ED burden is especially important in the era of ED overcrowding. This is a retrospective, propensity-matched, multi-center, observational study. Adult patients who received procainamide or amiodarone for atrial fibrillation/flutter in the ED at a Providence Hospital in the Oregon region from 2014 to 2024 were included. Patients were identified and screened through the use of EPIC Hyperspace and Slicer Dicer. Descriptive statistics were utilized to compare baseline characteristics. Rate of conversion to NSR and other categorical variables were compared with the chi-square test. Time to conversion to NSR and other continuous variables were compared with Student’s t-test. Linear or logistic regression analysis will be conducted to determine factors significantly associated with rate and/or time to conversion to NSR. Preliminary results were gathered with 22 patients receiving procainamide and 19 patients receiving amiodarone. There was no significant difference between incidence of atrial fibrillation (91.0% vs 78.9%) vs atrial flutter (9.0% vs 2.1%) between procainamide and amiodarone groups, respectively (p = 0.28). There was no significant difference between paroxysmal (50.0% vs 73.7%) vs new-onset (50.0% vs 26.3%) atrial fibrillation/flutter between procainamide and amiodarone groups, respectively (p = 0.062). Fifty percent of patients converted on procainamide, and 57.9% of patients converted on amiodarone (p = 0.613). For patients that did not convert to NSR, subsequent electrical cardioversion was successful in 100% of patients on procainamide and 26.3% of patients on amiodarone (p = 0.154). Time to conversion appeared to be shorter with procainamide (7.14 hours) vs amiodarone (16.4 hours), though this result did not achieve statistical significance likely due to lack of power (p = 0.069). Length of stay was significantly shorter in the procainamide group compared to the amiodarone group (10.1 vs 27.5 hours, p = 0.0059). Significantly more patients in the procainamide group were discharged from the ED compared to the amiodarone group (86.0% vs 31.6%, p < 0.001). Final conclusions will be shared when the formal analysis is completed. (IRB approved) Learning objectives: 1) Describe the impact of procainamide vs amiodarone on time to discharge for patients who present to ED with atrial fibrillation/flutter, 2) Compare the safety and effectiveness of procainamide versus amiodarone for atrial fibrillation/flutter Presentation Category: Cardiology/Emergency Medicine
-
Prescription Gardening: A Pilot Group Medical Visit for Spanish-Speaking Patients With Chronic Conditions
J. Stephanie Rodriguez, Jill Christensen, and Heidi David
Background Group medical visits (GMVs) have demonstrated benefits for patients with chronic conditions, including diabetes, obesity, and mental health disorders, by fostering peer support, improving health literacy, and enhancing patient engagement (Edelman et al., 2015; Riley et al., 2018). Community-based settings, such as gardens and teaching kitchens, offer additional advantages by promoting hands-on learning, stress reduction, and improved nutrition (Soga et al., 2017; Wolf & Zilverberg, 2018). However, Spanish-speaking patients often face barriers to accessing these services due to language limitations, lack of insurance coverage for certain providers (e.g., dietitians for obesity), and limited availability of bilingual healthcare professionals. This project aimed to assess patient satisfaction, build community, evaluate the financial feasibility of GMVs, and bridge gaps in care for Spanish-speaking patients by providing culturally and linguistically appropriate resources. Objectives • To evaluate the impact of garden-based group medical visits on patient satisfaction, health engagement, and perceived well-being. • To explore the financial and logistical feasibility of implementing GMVs as a sustainable model for primary care. • Assess interest in GMVs among bilingual patients with chronic conditions. • To assess potential collaborations with ancillary health services such as dietitians and community health workers. • Address healthcare gaps for Spanish-speaking patients by providing non-covered services. Methods: Setting: Community garden environment & community teaching kitchen Participants: Spanish-speaking patients with chronic conditions Structure: The GMV was 3 hours and was structured as a Level 3 billable visit with vitals collected at the beginning of the visit and group visits lead by a bilingual physician and a bilingual community health worker and conducted primarily in Spanish. Time was split between two locations the community garden and community kitchen. Participants engaged in multiple activities mindfulness exercises, group discussions on mental health, nutrition, and chronic disease, horticultural therapy, movement activities, and preparation of herbal and floral salves after harvesting. Data Collection: Patient testimonials, qualitative feedback, and provider observation Results • High patient satisfaction, with participants reporting increased confidence in managing chronic conditions and appreciation for culturally relevant care. • Positive community engagement, with participants expressing interest in ongoing GMVs. • Financial feasibility confirmed, as sessions could be billed similarly to in-clinic visits while incorporating services not typically covered by insurance (e.g., dietitian counseling for obesity). • Improved access to care, particularly for marginalized patients who otherwise would not qualify for certain services. • Initial group visit had projected to have 7 patients but due to heat wave patients were rescheduled. At the end of this, there were 3 participants that took part in this pilot group visit.
-

Characterization of Sarcoidosis at a Combined Rheumatology-Pulmonary Clinic
Megan Schermerhorn, MD and Julianna Desmarais, MD
Introduction: Sarcoidosis is a disease of unknown etiology characterized by formation of small clusters of inflammatory cells that form granulomas. Heterogenous and typically involves multiple organ systems with varying degrees of morbidity and mortality. Poorly defined treatment landscape. The purpose of this study was to characterize a cohort of sarcoidosis patients in a combined rheumatology-pulmonary clinic according to organ involvement and treatment over 5 years. Discussion: •Single center academic study of a that is the first of its kind. •Data highlights complexity and heterogeneity of patients with sarcoidosis and utility of combined rheumatology – pulmonary clinic. •65.3% of patients exhibited multiorgan involvement, which is higher than in other studies. •Treatment regimens were complex, in general, corticosteroids, methotrexate, and azathioprine were the most common DMARDS observed. In terms of biologics, anti-TNF alpha medications were most common. •More patients with multiorgan involvement were often treated with a biologic. Biologic use was in 40% of patients with cardiac involvement, and in 76.4% of patients with neurologic involvement. •70.5% of patients with neuro-sarcoid involvement were treated with three or more medications, indicating refractory disease. Limitations and Future Steps: •Treatment and overall standard of care guidelines for sarcoidosis is limited. Majority of data in the literature is limited to observational studies, generally small case series and case reports. •The overall variability in treatment regimen, particularly surrounding neurologic sarcoidosis indicates the need for further research to better identify the best medication approach, particularly in refractory cases where the usual approach is not efficacious. •Limited prospective data, no true standard of care for treatment regimens in sarcoidosis. •Our study did not evaluate for disease activity and the efficacy of treatment regimens.
-
Unveiling the Mystery: Paraneoplastic Syndrome Masquerading as Skin Thickening
Megan Schermerhorn, MD; Quian Leng; and Atish Dey
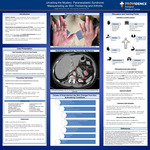
Introduction: Systemic sclerosis is a rare autoimmune disorder defined by skin thickening in the distal digits and is frequently accompanied by inflammatory arthritis. There are known mimics of systemic sclerosis, which present with similar sclerosis of the skin. Palmar fasciitis and polyarthritis syndrome (PFPAS) is a rare paraneoplastic syndrome that presents with progressive flexion contractures of the hands, inflammatory fasciitis, fibrosis, and generalized inflammatory arthritis. PFPAS is most associated with ovarian adenocarcinoma, and rarely associated with pancreatic adenocarcinoma. Early recognition of this rare syndrome was critical in identifying an asymptomatic pancreatic adenocarcinoma. Case Description: 58-year-old woman with osteoarthritis of multiple joints and 40 pack-year smoking history presented to her primary care physician with 2 months of joint pain and swelling in her hands and progressive skin thickening to the skin of the palms and pointer fingers. Stiffness and swelling lasted throughout the day, improved minimally with activity, and did not respond to physical therapy or non-steroidal anti-inflammatories. Examination showed thickening of the palmar skin in the hands with multiple tender subcutaneous nodules. There was also thickening of the right-hand pointer finger. Prescribed a methylprednisolone dose pack and referred to rheumatology. Discussion: Differentiating through History and Exam - Unlike systemic sclerosis PFPAS has no association with Raynaud’s phenomenon and scleroderma-specific antibodies are often negative. PFPAS tends to involve the palms. In this case, the fingers were involved prior to the palms, however, some fingers were spared while others proceeded rapidly to contractures, a pattern not consistent with scleroderma. The patient may have no other signs of systemic sclerosis, such as severe heartburn, matted telangiectasias, or calcinosis cutis. History of significant tobacco use increases the risk of various malignancies, including pancreatic malignancies. Response to Steroids Steroids may not improve skin thickening in systemic scleroderma; however, inflammatory joint pain should improve. It is important to consider underlying malignancy in similar cases of inflammatory polyarthritis when there is minimal response to high-dose steroids. Usefulness in Early Recognition - The bulk of the literature describing PFPAS occurs with ovarian adenocarcinoma, with only a few case reports associated with pancreatic adenocarcinoma. Ovarian and pancreatic malignancies are “silent killers,” which remain asymptomatic until late stages. PFPAS may be the first recognizable finding for patients with these malignancies.
-
When Calciphylaxis isn’t the Answer: Diagnostic Delay in an End Stage Renal Disease Patient with Severe Necrotic Wounds
Megan Schermerhorn, MD; Caroline McCulley; and Courtland Childers
Introduction: •Polyarteritis nodosa (PAN) is a necrotizing vasculitis that primarily affects medium-sized vessels, and less commonly small vessels •Skin findings in PAN include purpura, livedoid lesions, subcutaneous nodules, and necrotic ulcers. •Calciphylaxis is a syndrome of calcium deposition in the micro vessels of subcutaneous adipose tissue and dermis that results in painful skin lesions. •Skin findings in calciphylaxis may include induration, plaques, nodules, livedo, and purpura that progress to ulcers and black eschar. •Skin findings in calciphylaxis are a known mimic to PAN. Case Description: •50-year-old African American woman with history of end-stage renal disease (ESRD) and type-2 diabetes mellitus presented to the hospital with encephalopathy and necrotic ulcerating wounds with black eschar. •Numerous superficial wounds were located throughout the body including bilateral breasts, flank, legs, groin and toes. No subcutaneous nodules. •Wounds were not painful initially though progressed to severe debilitating tenderness. •Wound care consulted, no evidence of infectious process. •Given the appearance of the wounds and patient’s history of ESRD, calciphylaxis was suspected. Key Takeaways: •Calciphylaxis may mimic polyarteritis nodosa, gold standard diagnosis is based on biopsy. •While biopsy may cause risk of worsening calciphylaxis, this risk may be warranted in patients with severe ulcerating disease. •Anchoring bias is important to remember in the age of the electronic medical record and copy forward features. •Patients with skin of color have increased risk for misdiagnosis, delay in diagnosis, and treatment.
-

A potentially Cat-astrophic Missed Diagnosis: Systemic Autoimmune Disease or Something more Sinister
Cameron Smith, DO, MPH and Amy Dechet
Introduction: Disseminated bartonella infection has a mortality rate approaching 10%. Clinical presentation of bartonellosis can mimic systemic autoimmune disease. Traditional testing may not identify the organism, so a high degree of suspicion is warranted in patients with risk factors. Case Presentation: 32M with history of Tetralogy of Fallot with prosthetic pulmonary valve presented with fatigue x3 months. Reported severe splenomegaly, pancytopenia requiring transfusions, and renal failure requiring hemodialysis. Given concern for lupus-like syndrome, treated with steroids + cyclophosphamide. Persistent fevers despite broad antibiotics. Second opinion of renal biopsy: Postinfectious GN. Immunostains ruled out lupus-like disorder. Negative blood cultures, TEE, and serologies for HIV, EBV, CMV, hepatitis, coxiella, brucella, and bartonella. Takeaways: • Disseminated bartonellosis can mimic autoimmune diseases. • Patients with exposure to cats and with valvular heart disease are at highest risk. • False negatives common with serologies, blood cultures, and traditional PCR. • In patients with higher indices of suspicion, enhanced PCR’s at specialty labs, valve cultures, ddPCR, or cell-free DNA testing can enhance sensitivities.
-
Empowering Partners: Developing a Companion Program for Partners of Project Nurture
Peter St. George
Background: Project Nurture is a successful comprehensive program for pregnant people with substance use disorder that provides substance use treatment, prenatal care, in-hospital deliveries, ensuing postnatal care and pediatric care for the newborn. There currently is no complementary program to support the partners of those in Project Nurture, referred to inclusively and without gender as “fathers”. Objective: To develop a potential program structure for fathers that provides similar services to and is complementary with Project Nurture Providence Milwaukie. Methods: Via literature review, a qualitative survey of current Project Nurture patients, a needs assessment and assessment of existing services, we have identified gaps in care and propose a potential intervention. Results: Research evaluated revealed a strong connection between fathers with substance use disorder and suboptimal parenting skills and negative impacts on the child and mother. The survey of Project Nurture patients indicated a strong demand for father-supporting care, however no current programs in Portland meet this need. Nationally, several programs combine substance use treatment, parenting skills and social support. Additionally, Providence Milwaukie Family Medicine’s It MATTERS clinic is a virtual clinic treating those with substance use disorder. Conclusion: There is a clear link between fathers with substance use disorder and both suboptimal parenting skills and negative effects on their children and partners; however, no current programs locally address this. We propose a Project Nurture companion program serving fathers at Providence Milwaukie which integrates the pre-existing It MATTERS program with a parenting preparation and support program. Next steps for this project may include detailed program development and implementation and evaluation of a pilot program.
-
A Novel Method of Buprenorphine Induction Utilizing Buprenorphine extended-released Subcutaneous injection, intranasal naloxone and sublingual buprenorphine: A case report
Peter St. George, Josh Reagan, and Kasey Edwards Snider
Background: Current buprenorphine induction protocols were developed to treat heroin and prescription opioid use disorder. When applied to fentanyl, they are often unsuccessful. A new method for inducing buprenorphine called QuickStart involves simultaneous administration of intranasal naloxone and sublingual buprenorphine, with the ensuing withdrawal symptoms treated with additional sublingual buprenorphine. Administering buprenorphine extended-release subcutaneous injection (Sublocade) prior to QuickStart induction has not been detailed in medical literature. Objective: To describe a novel buprenorphine induction method utilizing Sublocade, intranasal naloxone and sublingual buprenorphine in a patient with fentanyl use disorder. Methods: Information was obtained by electronic medical record review, participation in the buprenorphine induction, interviews with the patient, and literature review. The patient read and signed an informed consent form, was provided a manuscript, and authorized publication. Results: A 22-year-old woman with fentanyl use disorder was induced on buprenorphine in our family medicine clinic with a combination of Sublocade, intranasal naloxone and sublingual buprenorphine. She experienced the expected precipitated withdrawal which peaked at thirty minutes and resolved at two hours. Reassessment at two months post-induction showed no return to fentanyl use and the patient has received regular administrations of Sublocade. Conclusion: Presented is the case of a patient who was treated in an ambulatory family medicine clinic for fentanyl use disorder with a novel buprenorphine induction method utilizing Sublocade followed by simultaneous administration of naloxone and sublingual buprenorphine. She has not returned to fentanyl use. This buprenorphine induction method may benefit patients unable to tolerate current buprenorphine induction methods and increases short-term buprenorphine compliance.
-
The Differential Expands: Ataxia from Paraneoplastic Cerebellar Degeneration
Dominic Thomas, MD and Amy Dechet
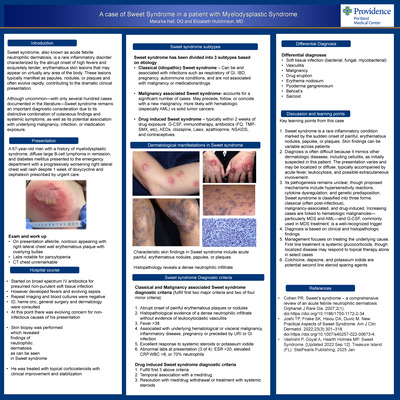
Introduction: Paraneoplastic cerebellar degeneration is a rare cause of cerebellar ataxia with a poor prognosis for neurologic recovery. The management of symptoms is dependent primarily upon timely diag-nosis and treatment of the underlying neoplasm. Herein, we present the diagnostic and treatment course of a patient with paraneoplastic cerebellar degeneration. Case: A 72-year-old woman with a past medical history of left mastectomy for high grade ER/PR negative Her2 positive invasive ductal carcinoma presented with progressively worsening dysarthria and ataxia over two months. A metabolic work up by her primary care physician was unrevealing. Breast MRI did not show recurrence of her cancer. During her visit with her oncolo-gist, the patient noted a ten-pound weight loss. At her first emergency department visit, exam revealed dysarthria but was an otherwise normal neurologic exam. MRI brain without contrast and MRA head and neck without contrast showed no evidence of ischemia, hemorrhage or mass effect. She was discharged home with the plan to follow up with outpatient neurology. Three days later, the patient presented to another emergency department and was found to be dysarthric but otherwise neurologically intact. CT head without contrast and CTA head and neck did not reveal a structural cause. MRI with and without contrast noted a non-specific T2 FLAIR hyperin-tense signal associated with the sulci or surface of the cerebellum. CSF showed elevated protein twice the upper limit of normal and a higher-than-normal fraction of lymphocytes. During her hospitalization she was noted to have worsening dysarthria, bilateral upper and lower extremity ataxia and development of diplopia for which she received 500mg methylprednisolone twice daily for three days and IVIG for five days. Symptoms were initially responsive but progressed further prompting five days of plasmapheresis. Symptoms did not remit. CA-125 was elevated at 253 U/mL and the CSF paraneoplastic panel was positive for anti-Yo antibody at 1:61440. A PET CT detected two para-aortic lymph nodes. Pathology from a total abdominal hysterectomy and bilateral salpingo-oophorectomy, peritoneal washing, and singular lymph node removal yielded carcinoma of mullerian origin in the lymph node alone. Steroids and cyclophosphamide were trialed for persistent neurologic symptoms. She received two cycles of docetaxel and carboplatin. The patient's care was transferred to a facility closer to family. Discussion: Paraneoplastic cerebellar degeneration is a rare cause of subacute cerebellar ataxia with an inci-dence of 0.41-0.89/100,000 person years2,3. Associated malignancies include most commonly small cell lung cancer, ovarian cancer, breast cancer and Hodgkin lymphoma. While several auto-antibodies have been identified as drivers of cerebellar degeneration, the anti-Yo antibody is predominantly associated with gynecological and breast cancers. Greater than 90% of these can-cers identified while alive or on autopsy4. Brain MRI rarely shows cerebellar enhancement, as seen in the described patient, and more typically is normal or shows cerebellar degeneration. Anti-Yo (purkinje cell cytoplasmic antibody type 1) can be detected in serum or CSF. It is the most commonly associated antibody intracellularly targeting the cerebellar degeneration-related 2-like (CDR2L) antigen within the Purkinje cells of the cerebellum6. When bound, it leads to cell death by inhibiting the ribosome to which it is bound. Once the diagnosis of paraneoplastic cerebellar ataxia is suspected, it is important to search for the source of the neoplasm since the most effec-tive antidote is treating the primary malignancy. Unfortunately, 75-80% of patients become and remain non-ambulatory with this condition, with delay of diagnosis likely contributing to poor outcomes4. There are anecdotal reports of neurologic improvement with IVIG, plasmapheresis, steroids, azathioprine, cyclophosphamide, and rituximab5. Albeit rare, it is important to be highly suspicious of autoantibody mediated neuronal degenerative diseases as symptom management depends on timely diagnosis and treatment. Conclusion: When work-up for more common causes of cerebellar ataxia is negative and/or if a paraneoplastic source is suspected, imaging and CSF testing can guide further evaluation. Once the diagnosis of para-neoplastic cerebellar ataxia is suspected, it is important to search for the source of the neoplasm since the most effective antidote is treating the primary malignancy. Albeit rare, it is important to be highly suspicious of autoantibody mediated neuronal degenerative diseases as symptom management depends on timely diagnosis and treatment
-
The Differential Expands: Ataxia from Paraneoplastic Cerebellar Degeneration
Dominic Thomas, MD and Amy Dechet
Introduction: Paraneoplastic cerebellar degeneration is a rare cause of cerebellar ataxia with a poor prognosis for neurologic recovery. The management of symptoms is dependent primarily upon timely diag nosis and treatment of the underlying neoplasm. Herein, we present the diagnostic and treatment course of a patient with paraneoplastic cerebellar degeneration. Case: A 72-year-old woman with a past medical history of left mastectomy for high grade ER/PR negative Her2 positive invasive ductal carcinoma presented with progressively worsening dysarthria and ataxia over two months. A metabolic work up by her primary care physician was unrevealing. Breast MRI did not show recurrence of her cancer. During her visit with her oncolo gist, the patient noted a ten-pound weight loss. At her first emergency department visit, exam revealed dysarthria but was an otherwise normal neurologic exam. MRI brain without contrast and MRA head and neck without contrast showed no evidence of ischemia, hemorrhage or mass effect. She was discharged home with the plan to follow up with outpatient neurology. Three days later, the patient presented to another emergency department and was found to be dysarthric but otherwise neurologically intact. CT head without contrast and CTA head and neck did not reveal a structural cause. MRI with and without contrast noted a non-specific T2 FLAIR hyperin tense signal associated with the sulci or surface of the cerebellum. CSF showed elevated protein twice the upper limit of normal and a higher-than-normal fraction of lymphocytes. During her hospitalization she was noted to have worsening dysarthria, bilateral upper and lower extremity ataxia and development of diplopia for which she received 500mg methylprednisolone twice daily for three days and IVIG for five days. Symptoms were initially responsive but progressed further prompting five days of plasmapheresis. Symptoms did not remit. CA-125 was elevated at 253 U/mL and the CSF paraneoplastic panel was positive for anti-Yo antibody at 1:61440. A PET CT detected two para-aortic lymph nodes. Pathology from a total abdominal hysterectomy and bilateral salpingo-oophorectomy, peritoneal washing, and singular lymph node removal yielded carcinoma of mullerian origin in the lymph node alone. Steroids and cyclophosphamide were trialed for persistent neurologic symptoms. She received two cycles of docetaxel and carboplatin. The patient's care was transferred to a facility closer to family. Discussion: Paraneoplastic cerebellar degeneration is a rare cause of subacute cerebellar ataxia with an inci dence of 0.41-0.89/100,000 person years2,3. Associated malignancies include most commonly small cell lung cancer, ovarian cancer, breast cancer and Hodgkin lymphoma. While several auto antibodies have been identified as drivers of cerebellar degeneration, the anti-Yo antibody is predominantly associated with gynecological and breast cancers. Greater than 90% of these can cers identified while alive or on autopsy4. Brain MRI rarely shows cerebellar enhancement, as seen in the described patient, and more typically is normal or shows cerebellar degeneration. Anti-Yo (purkinje cell cytoplasmic antibody type 1) can be detected in serum or CSF. It is the most commonly associated antibody intracellularly targeting the cerebellar degeneration-related 2-like (CDR2L) antigen within the Purkinje cells of the cerebellum6. When bound, it leads to cell death by inhibiting the ribosome to which it is bound. Once the diagnosis of paraneoplastic cerebellar ataxia is suspected, it is important to search for the source of the neoplasm since the most effec tive antidote is treating the primary malignancy. Unfortunately, 75-80% of patients become and remain non-ambulatory with this condition, with delay of diagnosis likely contributing to poor outcomes4. There are anecdotal reports of neurologic improvement with IVIG, plasmapheresis, steroids, azathioprine, cyclophosphamide, and rituximab5. Albeit rare, it is important to be highly suspicious of autoantibody mediated neuronal degenerative diseases as symptom management depends on timely diagnosis and treatment. Conclusion: When work-up for more common causes of cerebellar ataxia is negative and/or if a paraneoplastic source is suspected, imaging and CSF testing can guide further evaluation. Once the diagnosis of para neoplastic cerebellar ataxia is suspected, it is important to search for the source of the neoplasm since the most effective antidote is treating the primary malignancy. Albeit rare, it is important to be highly suspicious of autoantibody mediated neuronal degenerative diseases as symptom management depends on timely diagnosis and treatment
-
Evaluation of clinically non-preferred medications for the initial treatment of Type 2 diabetes within Providence Medical Group Oregon Region
Jake Turner, Pharm D; Bonnie Jiron; and Jack Huber
Abstract: Type 2 Diabetes Mellitus (T2DM) affects 1 in 10 American adults and increases a patient’s risk for developing complications, such as atherosclerotic cardiovascular disease, chronic kidney disease, and heart failure. Choosing the most optimal medications and controlling blood glucose can help prevent and/or reduce the risk of T2DM complications. Metformin has been the preferred initial agent for managing diabetes because it provides effective glycemic control, reduces the risk of microvascular complications, and lowers rates of cardiovascular-related mortality. In 2023, the American Diabetes Association recommended considering newer agents with cardiorenal and/or weight loss benefits, such as glucagon like peptide-1 agonists (GLP-1) or specific sodium glucose like transport-2 inhibitors (SGLT-2i), as preferred initial options independent of metformin use. While GLP-1, SGLT-2i and metformin are classified as clinically preferred initial treatments, it may be appropriate to use other medications as alternatives depending on patient specific factors and overall glycemic control. However, with the lack of cardiorenal risk reduction benefits and additional concerns for side effects, these agents are typically considered less preferred. There are various situations where using a clinically non-preferred medication might be suitable, although there is not much information available about the specific circumstances and reasons for this in practice. The purpose of this study is to describe prescribing patterns and rationale for the use of clinically non-preferred T2DM medications as initial therapy for T2DM within Oregon Providence Medical Group (PMG) primary care clinics. This is a multi-site, retrospective, descriptive analysis of patients who were prescribed a clinically non-preferred treatment as ini-tial therapy for T2DM between January 1st, 2023, to December 31st, 2024, either before or after the initiation of metformin. Patients to be analyzed were >18 years of age and from PMG primary care clinics in the Oregon region. Patients were excluded if pregnant, imprisoned, or being cared for at a residency teaching clinic. Epic electronic medical records were queried by a data analyst to generate a report of patients with an initial clinically non-preferred treatment for T2DM. Approximately 200 patients will be randomly selected for manual chart review to help determine the rationale for initiating non-preferred treatments along with clinical appropriateness based on patient specific factors. Descriptive statistics will be used to analyze the baseline characteristics of the study population, prescribing patterns, and rationale. Results and Conclusions will be shared when the project is completed. (IRB approved)
-
Oral BEta-Lactam Stepdown to treat gram negative bacteremia in patienTs with obesitY (OBESITY)
Victoria Wilson, PharmD; Greg Tallman; and Emily Fox
Abstract: Oral stepdown therapy for uncomplicated Gram-negative bloodstream infection is a widely accepted practice supported by randomized controlled and observational data. Fluoroquinolones, sulfamethoxazole-trimethoprim, and certain beta-lactams are frequently used for oral stepdown. Pharmacokinetic changes due to obesity may increase treatment failure, particularly with beta-lactams. However, current studies of oral stepdown for Enterobacterales bloodstream infections have not evaluated the impact of obesity on treatment failure. The purpose of this study was to assess whether patients with obesity (defined as BMI ≥ 30 kg/m2) receiving oral step-down therapy for Enterobacter-ales bacteremia have increased clinical treatment failure compared to nonobese patients. This was a multicenter retrospective study of adult patients hospitalized with monomicrobial Enterobacterales bloodstream infections between September 2021 to September 2024. Patients were excluded if they received > 4 days of IV therapy. Patient data were electronically extracted from the electronic health record. The primary outcome was clinical treatment failure, defined as a composite of 30-day recurrence, 30-day infection-related readmis-sion, and 30-day all-cause mortality. Secondary outcomes included duration of therapy and antibiotic selection. This study was reviewed by the institutional review board and deemed exempt. A total of 2,390 blood cultures were identified during the study period and 1,099 were included. An interim analysis was completed. Predominant pathogens included Escherichia coli (774/1,099, 70.4%) and Klebsiella pneumoniae (143/1,1099, 13%). A total of 221 (20.1%) patients met the composite primary outcome. Of the nonobese patients, 148 met the composite primary outcome of treatment failure (148/674, 21.9%) vs 73 patients with obesity (73/425, 17.2%). Overall, 17/1099 (1.5%) experienced recurrence, 135 (12.3%) patients readmitted, and 86/1099 (7.8%) patients expired. Further results and conclusions will be shared when the project is completed. Learning Objectives: Evaluate the association between treatment failure and obesity in adult patients receiving oral step-down therapy for Enterobacterales bacteremia. Presentation Category: Infectious Diseases
-
Methicillin-Resistant Staphylococcus Aureus Nasal Testing Negative Predictive Value for Skin and Soft Tissue Infections
Sabra Woodruff, PharmD
Learning Objectives: 1. Assess the importance of MRSA nasal screening versus culture data when it comes to guiding therapy for SSTI management. 2. Identify if there are any infection characteristics that significantly impact outcome of predictive values of MRSA NAAT PCR testing. Abstract: Introduction Methicillin-Resistant Staphylococcus aureus (MRSA) NAAT PCR has been a valuable tool for de-escalating vancomycin, including for management of skin and soft tissue infections (SSTIs). However, providers have reported instances where a negative MRSA NAAT has led to narrowing antibiotics, but the wound culture revealed MRSA growth. Due to the short time for MRSA nasal swab result compared to wound culture result, this could be a common occurrence in the hospital setting. Previous research shows MRSA NAAT negative predictive value for all SSTI to be anywhere between 80% to 98.4%. In this study, we assessed the negative predictive value of MRSA NAAT PCR with SSTIs. Methods Retrospective, single center study evaluating 162 patients with diagnosis of SSTI between November 2022 to January 2025. Analyzed impact of data using sensitivity, specificity, positive predicative value, negative predictive value, positive likelihood ratio, and negative likelihood ratio. Results: This population included a majority of purulent infections (n=134, 82.7%) and patients with a diagnosis of cellulitis (n=65, 40.1%). Of the pa-tients included in this study, 92 (56.8%) had a negative MRSA NAAT PCR with no MRSA growth, 37 (22.8%) had a positive MRSA NAAT PCR with MRSA growth, 15 (9.3%) had a negative MRSA NAAT PCR with MRSA growth, and 18 (11.1%) had a positive MRSA NAAT PCR with no MRSA growth. This data calculated a negative predictive value (NPV) of 86% (95% CI, 77.6-91.7%) and a positive predicative value (PPV) of 67.3% (95% CI, 53.2-79%). Conclusion: MRSA NAAT PCR testing is a valuable tool for de-escalation; however, other factors need to be taken into consideration prior to use for de-escalation of vancomycin in the setting of SSTIs specifically
-
Evaluation of extended-interval thyroid function monitoring during pembrolizumab treatment
Hanna Yoon, PharmD and Heather Beugli
Abstract: Thyroid dysfunction is a common immune-related toxicity in patients treated with immune checkpoint inhibitors, with hypothyroidism being more common than hyperthyroidism. The National Comprehensive Cancer Network (NCCN) Guidelines conditionally recommend extending thyroid function monitoring from every 4 to 6 weeks to every 12 to 18 weeks in patients without baseline thyroid abnormalities. Currently, the Providence Cancer Institute Franz Clinic checks thyroid function every treatment cycle. A treatment cycle for a common immune checkpoint inhibitor called pembrolizumab is 3 weeks for fixed-dose 200 mg. This study aims to evaluate whether reducing the frequency of thyroid-stimulating hormone (TSH) and free thyroxine (T4) lab monitoring impacts patient management in terms of safety and provides potential cost savings. This single-institute retrospective observational study includes patients aged 18 years or older who received pembrolizumab 200 mg between September 1, 2023, and August 31, 2024. Patients were excluded if they received pembrolizumab for research purposes, had fewer than four doses, had baseline thyroid function abnormalities, or were taking thyroid hormone replacement prior to pembrolizumab treatment. The primary endpoint for determining patient safety was assessed using a Kaplan-Meier survival analysis, comparing 3-week monitoring with extended intervals by evaluating the number of missed or delayed detections of thyroid abnormalities. Compared with 3-week monitoring, 6-week monitoring identified 9 additional cases (p = 0.14), 11 cases with 12-week monitoring (p = 0.08), 12 cases with 18-week monitoring (p = 0.05), and 17 cases with 21-week monitoring (p < 0.05). Among the 98 patients, 42% (n=41) developed thyroid abnormalities after receiving pembrolizumab treatment. Fourteen had subclinical hyperthyroidism, eleven had subclinical hypothyroidism, and sixteen had clinical hypothyroidism. None of the patients with subclinical hypo- or hyperthyroidism were found to have received drug therapy. No cases of clinical thyroid level abnormalities occurred within the first 42 days of treatment. Three patients developed clinical hypothyroidism between 42 and 84 days, while thirteen patients developed clinical hypothyroidism after 84 days. The median time from the first dose to the onset of any type of abnormal thyroid function was 86 days. The secondary endpoint estimated yearly cost savings if extended lab monitoring was utilized in the treatment group. Cost savings of $75,590.67 was found with 6-week monitoring, $113,386.00 with 12-week monitoring, and $125,984.44 with 18-week monitoring. In conclusion, extending thyroid function monitoring to every 12 weeks for patients receiving pembrolizumab without baseline thyroid abnormalities was found to be safe and to provide significant cost savings for patients. (IRB exempt) Learning objectives: Determine whether extending the thyroid function monitoring interval is safe for patients treated with pembrolizumab who do not have baseline thyroid abnormalities. Assess the potential cost savings for patients when using extended-interval thyroid function monitoring. Presentation category: Oncology/Hematology
-
Efficacy and outcomes associated with carbapenem treatment during a resistant Shigellosis cluster in Portland
Zach Zhang, Emily Fox, and Greg Tallman
Abstract: Shigella has caused multiple diarrheal illness outbreaks across the Portland metro area over the past decade. These infections have become both more numerous and difficult to treat with an increasing proportion of extensively drug resistant (XDR) strains. Consequently, hospitals within our health system have utilized short courses of carbapenems for patients with severe symptoms. This project is designed to compare clinical outcomes of patients treated with carbapenems to those treated with traditional first-line antibiotics or supportive care. Additionally, we aimed to better characterize the risk factors and prevalence of XDR shigellosis within our health system. This was a multi-center retrospective cohort study across five Providence hospitals within the Portland-metro area that was approved by the Institutional Review Board. All patients aged 18 years or older and diagnosed with Shigellosis from October 2023 to August 2024 were screened for inclusion. Patients who tested positive for Clostridium difficile or had a positive gastrointestinal (GI) multiplex result with an organism other than Shigella were excluded. The two comparator groups were those treated with carbapenems versus those treated with alternative antibiotics or supportive care alone. The primary outcome was number of days until resolution of symptoms as defined by less than 3 recorded stool occurrences in one day. Patients started on antibiotics after their documented resolution of symptoms or seen only in the emergency department were not included in the final analysis. Other data points collected included patient characteristics such as age, sex, race/ethnicity, housing status, HIV status, presence of comorbid GI disease, fever status, white blood cell count (WBC), and mean arterial pressure (MAP). For data analysis, a student T-test was used to assess the primary outcome. Sixty-four patients met inclusion criteria. Twenty-nine (45%) were treated with carbapenems, while 35 (55%) were treated with non-carbapenem antibiotics or supportive care only. Mean time to resolution of symptoms was not significantly different in the carbapenem versus non-carbapenem group (42.7 vs 30.6 hours, p = 0.41). Patients treated with car-bapenems had longer lengths of hospital stay (167.5 vs 78.7 hours) compared to patients treated with non-carbapenem antibiotics. WBC, temperature, and MAP on presentation were similar between groups. Antibiotic susceptibilities were performed on 12 (19%) samples; 1/11 (9.1%) were resistant to ceftriaxone, 3/12 (25%) were resistant to ciprofloxacin. Treating shigella infections with carbapenems was associated with longer resolution of symptoms when com-pared with non-carbapenem antibiotics, despite similar infectious markers at time of presentation between the two groups. Learning objectives: Assess the effectiveness of using carbapenems as first-line therapy in treating XDR shigellosis. Describe clinical characteristics of Shigella infections within the Portland-metro area. Presentation Category: Infectious Diseases
-
From Hormones to Pancreatitis: A Case of Estrogen-Induced Hypertriglyceridermia
Kyaw Zin (Kennis) Htet, MD; Michael Lefor, MD; and B C. Clark, MD
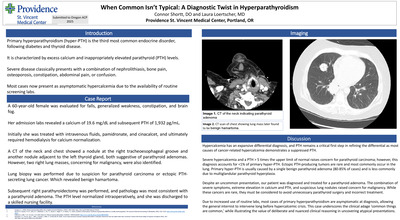
Introduction: Hormonal replacement therapy (HRT) for transgender women, also known as gender-affirming hormone therapy (GAHT), is designed to align physical characteristics with gender identity. Potential risk associated with feminizing hormone therapy with estradiol include venous thromboembolism, cardiovascular disease and changes in lipid profile. We present a case of estrogen replacement therapy induced hypertriglyceridemia causing acute pancreatitis in a young transgender woman. Case Presentation: A 30-year-old transgender woman on estrogen and progesterone replacement therapy, as well as history of hypertension and MELAS syndrome admitted with 2-day history epigastric pain, nausea, and decreased urination. Notably, her estradiol dosage had recently increased from 6 mg to 8 mg five months prior. Discussion: Acute pancreatitis is a potentially life-threatening condition with significant morbidity and mortality, often resulting from gallstones or alcohol use. Hypertriglyceridemia, though a less common cause, can trigger pancreatitis by increasing free fatty acid production, leading to pancreatic inflammation and injury. The underlying mechanisms of hypertriglyceridemia-induced pancreatitis are not fully understood but are believed to involve hydrolysis of triglycerides into toxic free fatty acids, causing direct pancreatic injury, endothelial damage, calcium overload, and a pronounced inflammatory response. Estrogen therapy, particularly oral formulations, has been associated with elevated plasma triglyceride levels due to its effects on hepatic lipid metabolism. In this case, estrogen-induced hypertriglyceridemia was the likely precipitant of acute pancreatitis, exacerbated by the patient’s pre-existing conditions, including MELAS syndrome and hypertension. The increase in estradiol dosage may have further contributed to the rise in triglyceride levels. Clinicians should routinely monitor triglyceride levels in transgender women receiving estrogen therapy, especially in those with predisposing conditions. Transdermal estradiol, as used in this patient post-discharge, may pose a lower risk of hypertriglyceridemia due to reduced first-pass hepatic metabolism. Early intervention, lipid control, and switching to safer formulations can mitigate the risk of serious complications like pancreatitis.
Printing is not supported at the primary Gallery Thumbnail page. Please first navigate to a specific Image before printing.